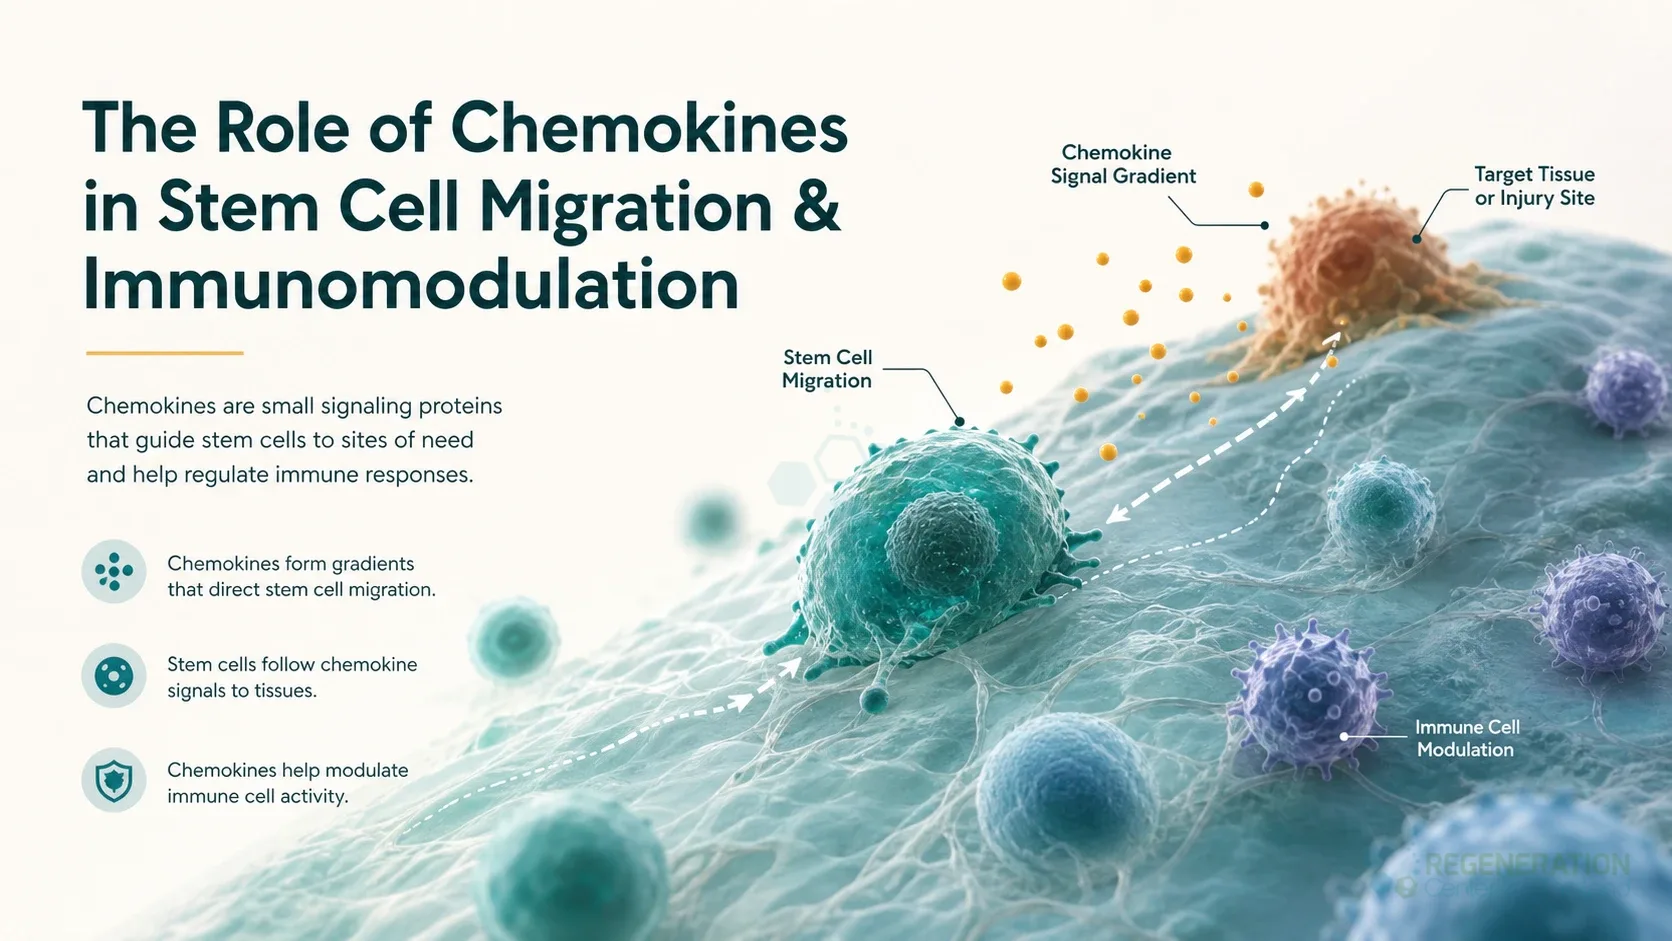
Chemokines are small secreted proteins that make cells move. A cell releases them, they stick to the surfaces of cells and to the matrix around them, and cells carrying the matching receptor crawl up the resulting concentration gradient. They control where white blood cells go in health and in disease, and the same signals guide blood stem cells to the bone marrow. This page covers what chemokines are, how they are classified, how they signal, what goes wrong with them, and the medicines that act on their receptors. The journey infused stem cells make, and how far they actually get, is on our page on homing and cell migration.
Understanding the Basics of Chemokines
A chemokine is a small protein held in shape by disulfide bonds between cysteine amino acids: a three-stranded sheet, a helix lying over it, and a short loose tail at one end that is what actually switches the receptor on.[1] Platelet factor 4, now called CXCL4, was one of the first members of the family to be sequenced: its 70 amino acids were reported in 1977.[2]
Chemokines carry two names in the literature: an older working name (for example interleukin-8, RANTES, SDF-1) and a systematic name based on the class and a number (CXCL8, CCL5, CXCL12). The systematic names are used below.[1]
Chemokine Classifications and Types
The classes are defined by the spacing of the first two cysteines near the start of the protein.[1] Receptors are named after the class of chemokine they mainly bind: there are 18 conventional receptors, 10 CCRs, 6 CXCRs and one each of CX3CR and XCR, all of them G protein-coupled receptors.[1]
| Class | Arrangement of the first two cysteines | Examples (systematic and older name) | Main receptor |
|---|---|---|---|
| CC | Next to each other | CCL2 (MCP-1); CCL5 (RANTES); CCL21, which guides dendritic cells along lymphatic vessels and into lymph nodes | CCR2; CCR5; CCR7[1] |
| CXC | One amino acid between them | CXCL8 (interleukin-8); CXCL12 (SDF-1), which holds blood-forming stem cells in the marrow | CXCR1 and CXCR2; CXCR4[1] |
| CX3C | Three amino acids between them | CX3CL1 (fractalkine), the only member; it sits on the cell surface on a stalk and can be cut free | CX3CR1[1] |
| XC | The first cysteine is missing | XCL1 and XCL2 (lymphotactin), the only two in humans | XCR1[1] |
Several chemokines often bind the same receptor and one chemokine often binds several receptors, so the system has built-in overlap.[1] A separate group, the atypical chemokine receptors (ACKR1 to ACKR4), bind chemokines but do not set off the usual signalling: they soak chemokines up, move them across tissue or shape the gradient. ACKR3, for example, controls the CXCL12 and CXCR4 pair by scavenging CXCL12.[1]
The Process of Chemokine Signaling
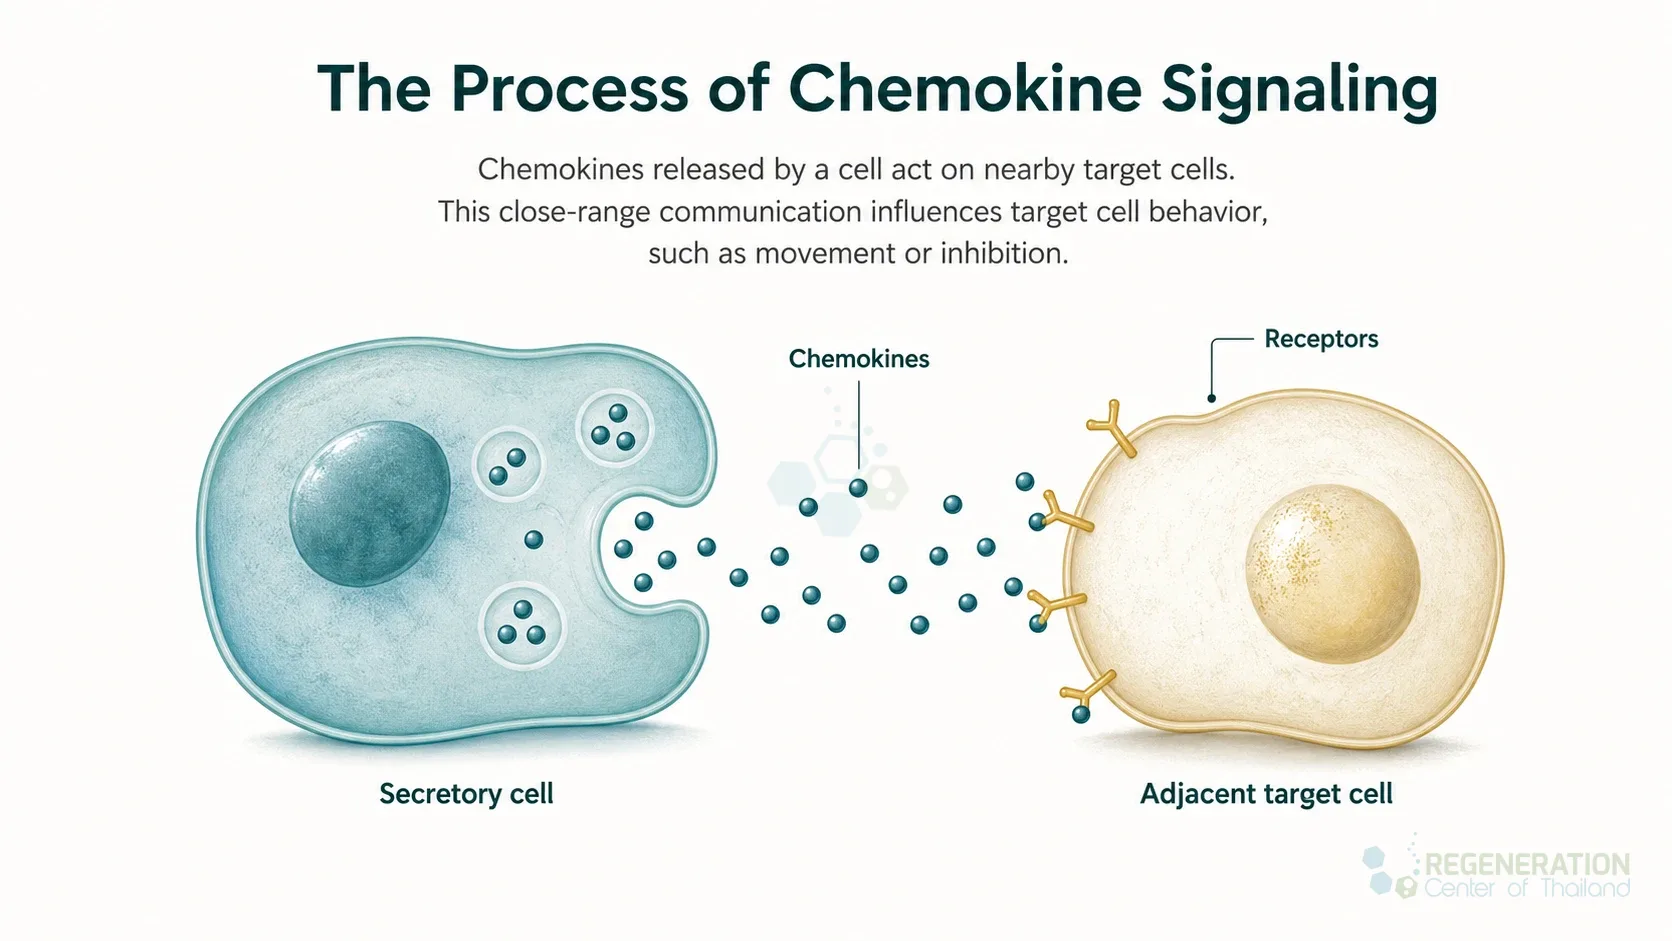
Released chemokines do not simply drift away. They bind sugar chains called glycosaminoglycans on cell surfaces and in the matrix, which holds them in place and builds a gradient a moving cell can read.[1] A chemokine’s loose tail then engages its receptor, a G protein-coupled receptor, and the signal passes inside through G proteins and other routes including beta-arrestins and JAK-STAT pathways, ending in the cell crawling toward the source, sticking more firmly to the vessel wall, or other responses.[1]
The signal is tuned after release. Enzymes trim amino acids from a chemokine’s ends, which can make it more active, inactivate it or turn it into a blocker of its own receptor: trimming by matrix metalloproteinases strengthens CXCR2 ligands but inactivates CXCL12, and turns some CCR2 ligands into antagonists.[1] This local signalling is one form of the paracrine signaling described on its own page.
The Role of Chemokines in Immunity
Chemokines do two jobs. Some organise the everyday traffic of immune cells: through the receptor CCR7, dendritic cells follow CCL21 into lymphatic vessels and on into lymph nodes, where adaptive immune responses begin; CXCR2 and CXCR4 control the exit of neutrophils from the marrow and their return to it; monocytes use CX3CR1 to patrol the walls of blood vessels. Others are made when tissue is infected or damaged and bring in the cells that deal with it.[1] Which cell answers a given call depends on which receptors it carries.
Chemokines are a subgroup of the cytokines, the larger family of signalling proteins that also includes the interleukins, interferons and tumour necrosis factors. What marks chemokines out is that their main job is to direct movement.[1] The wider cytokine system and the drugs that act on it are described on our page on immunomodulation, and the healing response itself on our page on inflammation.

Disorders Linked to Chemokine Dysfunction
- HIV infection. CCR5 and CXCR4 are the co-receptors HIV uses to enter cells, after its envelope protein has bound CD4. People who carry two copies of the non-functional delta-32 version of CCR5 are strongly protected against infection, and carrying one copy is linked, in most groups studied, to slower progression to AIDS.[1]
- WHIM syndrome. A rare inherited immune disorder (warts, low antibody levels, infections and neutrophils stuck in the marrow) caused by mutations that leave the receptor CXCR4 switched on too strongly.[1] Mavorixafor, a CXCR4 blocker, is approved for it (see below).[3]
- Inflammatory disease. Chemokines recruit the cells that drive chronic inflammation, which is why their receptors are studied as drug targets.[1]
- Cancer. Cancer cells that are not immune cells can come to carry chemokine receptors and respond to chemokines, which can encourage local invasion, spread to the draining lymph nodes and seeding of distant tissues.[1] This is covered on our page on cancer stem cells.
Medicines That Act on Chemokine Receptors
As of November 2026, five medicines approved in the United States act directly on chemokine receptors. They show what the system can be used for, and also how narrow the proven uses are.
| Drug | Target | Approved use |
|---|---|---|
| Plerixafor (Mozobil) | Blocks CXCR4, so CXCL12 (SDF-1) can no longer bind it | With filgrastim (G-CSF), to move blood stem cells out of the marrow into the bloodstream so they can be collected and given back to patients with non-Hodgkin lymphoma or multiple myeloma.[4] This is the same CXCL12 and CXCR4 bond that holds those cells in the marrow |
| Motixafortide (Aphexda) | Blocks CXCR4, so CXCL12 can no longer bind it | With filgrastim (G-CSF), to move blood stem cells into the bloodstream for collection and later transplantation back into patients with multiple myeloma. Approved in the United States in 2023.[5] |
| Mavorixafor (Xolremdi) | Blocks CXCR4; taken by mouth | WHIM syndrome in people aged 12 and older, to raise the number of mature neutrophils and lymphocytes in the blood. Approved in the United States in 2024.[3] |
| Maraviroc (Selzentry) | Blocks CCR5 | With other antiretroviral drugs, for HIV-1 infection, but only where the virus uses CCR5 to enter cells; it is not recommended when the virus uses CXCR4.[6] |
| Mogamulizumab (Poteligeo) | An antibody against CCR4 | Relapsed or refractory mycosis fungoides or Sézary syndrome, two cancers of T cells, after at least one previous whole-body treatment. It marks CCR4-carrying cells for destruction by immune cells.[7] |
Plerixafor and motixafortide are the clearest link between chemokine biology and cell therapy: added to G-CSF, the standard mobilising medicine, they release more blood stem cells for collection by breaking the chemokine bond that normally keeps those cells in the marrow. Collection by apheresis and the transplant itself are described on our page on hematopoietic cell transplant.
Chemokines in Stem Cell Medicine
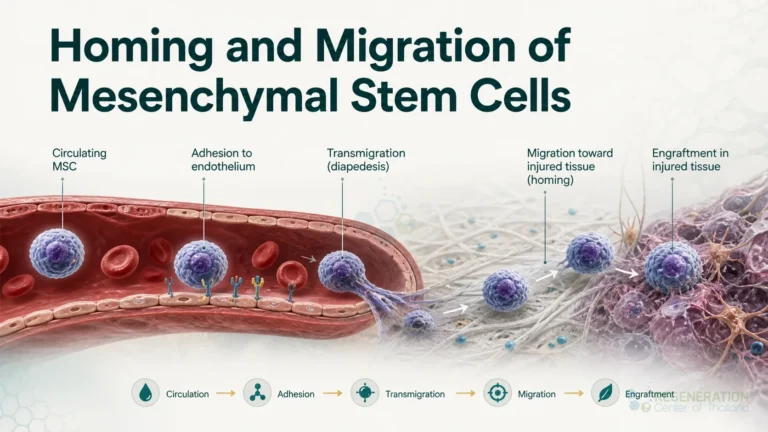
CXCL12 and its receptor CXCR4 help hold blood-forming stem cells in the marrow and help guide transplanted ones back to it.[4] Cultured mesenchymal stromal cells carry the same receptor, but only a small fraction of them carry a working copy, and in laboratory migration tests that receptor was important for their movement toward bone marrow.[8] Mesenchymal stromal cells also release chemokines themselves, among other factors, as part of their secretome. In mice, chemokines released by these cells drew T cells close enough for nitric oxide from the same cells to suppress them, and the cells prevented graft-versus-host disease.[9] Those immune effects are set out on our page on immunomodulation, and the full set of signalling molecules on our secretome page.
Published Clinical Citations
[1] ^ Hughes CE, Nibbs RJB. A guide to chemokines and their receptors. FEBS Journal. 2018;285(16):2944-2971. https://doi.org/10.1111/febs.14466
[2] ^ Deuel TF, Keim PS, Farmer M, Heinrikson RL. Amino acid sequence of human platelet factor 4. Proceedings of the National Academy of Sciences of the USA. 1977;74(6):2256-2258. https://doi.org/10.1073/pnas.74.6.2256
[3] ^ X4 Pharmaceuticals, Inc. XOLREMDI (mavorixafor) capsules, for oral use. US prescribing information; initial US approval 2024. DailyMed set ID 7f3a5ee3-ca73-4876-85a0-ed1e108a2237. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=7f3a5ee3-ca73-4876-85a0-ed1e108a2237
[4] ^ Sanofi-aventis US LLC. MOZOBIL (plerixafor) injection, for subcutaneous use. US prescribing information. DailyMed set ID 0ed08d2b-5051-46b2-aa37-1d6275bf9003. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=0ed08d2b-5051-46b2-aa37-1d6275bf9003
[5] ^ BioLineRx USA Inc. APHEXDA (motixafortide) for injection, for subcutaneous use. US prescribing information; initial US approval 2023. DailyMed set ID f7cdc584-ebf0-a68e-e053-6294a90a9ea9. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=f7cdc584-ebf0-a68e-e053-6294a90a9ea9
[6] ^ ViiV Healthcare Company. SELZENTRY (maraviroc) tablets, for oral use. US prescribing information. DailyMed set ID 46f30ac5-c96b-429e-976d-8c5ee1c0761b. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=46f30ac5-c96b-429e-976d-8c5ee1c0761b
[7] ^ Kyowa Kirin, Inc. POTELIGEO (mogamulizumab-kpkc) injection, for intravenous use. US prescribing information. DailyMed set ID e53960ab-42a1-40d1-9c7d-eb013fe7f18f. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=e53960ab-42a1-40d1-9c7d-eb013fe7f18f
[8] ^ Wynn RF, Hart CA, Corradi-Perini C, et al. A small proportion of mesenchymal stem cells strongly expresses functionally active CXCR4 receptor capable of promoting migration to bone marrow. Blood. 2004;104(9):2643-2645. https://doi.org/10.1182/blood-2004-02-0526
[9] ^ Ren G, Zhang L, Zhao X, et al. Mesenchymal stem cell-mediated immunosuppression occurs via concerted action of chemokines and nitric oxide. Cell Stem Cell. 2008;2(2):141-150. https://doi.org/10.1016/j.stem.2007.11.014