
Peripheral blood stem cells (PBSCs) are blood-forming (hematopoietic) stem cells collected from the circulating blood. These stem cells give rise to all blood cells; they live mainly in the bone marrow, and only small numbers circulate in the blood.[1] For a transplant, medicines are first used to move them out of the bone marrow into the bloodstream (mobilization), and a machine then separates them from the blood (apheresis).[2] Most of the blood-forming stem cells used in transplants are now collected this way rather than from the marrow itself.[3] Transplantation of these cells is an established treatment for certain blood cancers and disorders of blood production. It is a different thing from the many “stem cell” products offered for other conditions without approval, which the US Food and Drug Administration warns about whether the cells come from the patient’s own body or from someone else.[4]
How to harvest stem cells from peripheral blood
Mobilization
The standard mobilizing medicine is filgrastim, a granulocyte colony-stimulating factor (G-CSF). For collection from a patient’s own blood, its US label gives 10 micrograms per kilogram a day by injection under the skin for at least 4 days before the first apheresis, continued until the last one.[5] Mobilization can also combine chemotherapy with G-CSF, as in a Thai series that used cyclophosphamide and G-CSF.[6] Filgrastim can trigger severe, sometimes fatal sickle cell crises in people with sickle cell disease, and its label warns of this.[5] Two further medicines block the CXCR4 receptor, which helps anchor stem cells in the marrow, and are approved in the United States for use together with filgrastim before an autologous transplant: plerixafor for non-Hodgkin lymphoma and multiple myeloma,[7] and motixafortide for multiple myeloma.[8] Plerixafor is effective but costly; one large US transplant center describes using laboratory tests during mobilization and the yields of early collections to decide when to add it.[9] More on the growth factor itself is on our page on granulocyte colony-stimulating factor.
Apheresis
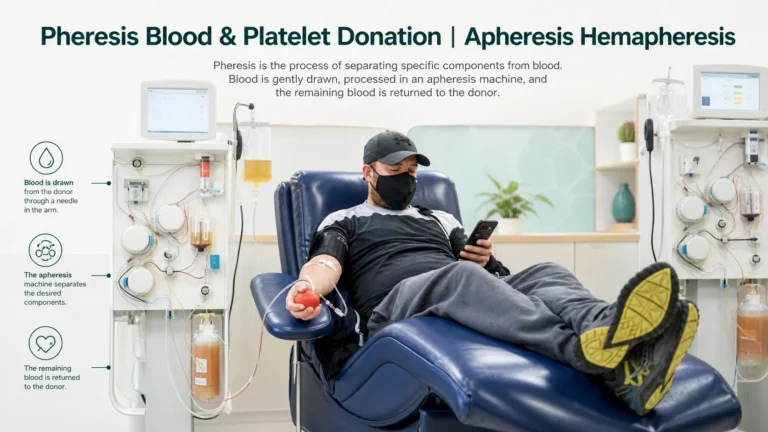
Blood is drawn through an intravenous line and passed through a machine that removes the white-cell fraction containing the stem cells; the rest of the blood is returned.[2] A peripheral vein is the usual access.[11] When veins cannot give enough flow, a central venous catheter is placed; in a prospective study of 2,408 unrelated donors, women needed one more often than men (17 against 4 percent).[10] A retrospective study of 150 collections found that drawing blood from a peripheral artery, with return through a vein, collected a similar number of CD34-positive stem cells as vein access, with fewer low-pressure alarms.[11] For an autologous transplant the collected cells are frozen until they are needed.[2]
Side Effects of Collection
In the 2,408-donor study, nearly all donors had bone pain from filgrastim, 1 in 4 had significant headache, nausea or citrate toxicity, and 0.6 percent had serious unexpected toxicities; all recovered completely, and no late effects attributable to donation were found.[10] The filgrastim label lists bone pain, fever and headache as the common reactions during mobilization and warns of splenic rupture, including fatal cases; pain in the upper left abdomen or the shoulder needs prompt assessment.[5]
Peripheral Blood Stem Cells Transplants
A transplant has three main steps.
- Conditioning. The patient receives high-dose chemotherapy, radiation or both to kill cancer cells and the remaining marrow, or, in a reduced-intensity transplant, lower doses that allow older or less fit patients to be treated.[2] Autologous transplants for multiple sclerosis have used a nonmyeloablative regimen (cyclophosphamide with antithymocyte globulin) aimed at the immune system rather than the whole marrow.[12]
- Infusion. The cells, thawed if they were frozen, are given into the bloodstream, usually through a central venous catheter, much like a blood transfusion.[2]
- Engraftment. The cells travel to the bone marrow and take the place of the cells destroyed by treatment. Blood counts recover first; full recovery of the immune system takes several months after an autologous transplant and 1 to 2 years after an allogeneic one.[3] How cells find their way to the marrow is described on our page on homing and cell migration.
In an autologous transplant the patient’s own cells are returned, with a small risk that cancer cells collected with them are given back. In an allogeneic transplant the donor’s white cells can attack the patient’s tissues (graft-versus-host disease) and can also attack remaining leukemia cells.[3]
Blood, Marrow and Cord Blood Compared
| Mobilized peripheral blood | Bone marrow | Umbilical cord blood | |
|---|---|---|---|
| How collected | Injections for several days, then apheresis[2] | Minor operation under general anesthesia; marrow drawn from the back of both hip bones[2] | From the cord after birth, then frozen[2] |
| Serious events for donors | 0.56 percent[13] | 2.38 percent[13] | Not part of that comparison |
| Graft failure (unrelated donors) | 3 percent[14] | 9 percent[14] | Not part of that trial |
| Chronic graft-versus-host disease at 2 years (unrelated donors) | 53 percent[14] | 41 percent[14] | Not part of that trial |
Cord blood cells are immature, so a perfect tissue match matters less, but a unit holds fewer stem cells, so blood counts take much longer to recover.[2] The donor figures come from 2,726 marrow and 6,768 blood stem cell donors in the US registry, who also had no difference in later cancer, autoimmune illness or thrombosis.[13] The graft figures come from a phase 3 trial of 551 patients, in which survival at 2 years did not differ significantly (51 percent with blood stem cells and 46 percent with marrow).[14] The chance of finding an optimally matched unrelated adult donor ranges from 75 percent for white patients of European descent to 16 percent for black patients of South or Central American descent.[15]
Where PBSC Transplants Are Used
- Cancers. Stem cell transplants are used most often for cancers of the blood cells, such as leukemia, lymphoma, multiple myeloma and myelodysplastic syndromes, and also for neuroblastoma, Ewing sarcoma, brain tumors that have come back in children, and germ cell and testicular cancers.[3]
- Disorders of blood production and immunity. These include aplastic anemia, congenital neutropenia, severe immune system illnesses, sickle cell anemia and thalassemia.[2] In two children with Wiskott-Aldrich syndrome, an inherited immune deficiency, blood stem cells mobilized with G-CSF and collected from their brothers engrafted without graft-versus-host disease.[16]
- Gene therapy. Two US-approved treatments for sickle cell disease, CASGEVY and LYFGENIA, are made from the patient’s own collected blood stem cells, which are genetically modified and given back after high-dose chemotherapy as part of a stem cell transplant.[17] More on these methods is on our page on gene therapies.
- Severe autoimmune disease. Autologous transplants have been tested in randomized trials. In 110 people with relapsing-remitting multiple sclerosis who kept relapsing on treatment, disability progressed in 3 patients after transplant and in 34 who switched drugs (55 randomized to each group); the authors called the study preliminary.[12] In 75 adults with severe scleroderma, event-free survival at 72 months was 74 percent after transplant against 47 percent with cyclophosphamide, with treatment-related deaths in 6 percent of the transplant group.[18] An overview of these conditions is on our page on autoimmune diseases.
Not every use has held up. High-dose chemotherapy with a blood stem cell transplant was also tried for breast cancer, for example in a single-center series of 20 women with high-risk breast cancer in Thailand.[6] In a randomized trial of 199 women with metastatic breast cancer, the transplant did not improve survival (32 percent at 3 years, against 38 percent with conventional chemotherapy).[19] For high-risk breast cancer treated after surgery, an analysis of individual patient data from 15 randomized trials with 6,210 patients found longer relapse-free survival with the transplant but no improvement in overall survival.[20]
Other Cell Types and Birth Tissue
Mesenchymal stromal cells (MSCs) are a different cell type. They are found in bone marrow, fat and umbilical cord tissue, and form bone, cartilage and fat cells rather than blood.[21] MSCs from fat and from dental pulp do not rebuild the blood and immune system, so they are not an alternative to a blood stem cell transplant. Umbilical cord tissue holds MSCs in Wharton’s jelly, the gel around the cord’s blood vessels.[21] Collection takes place immediately after the birth of a baby, during which the umbilical cord is clamped, cut, and separated from the newborn. The cord tissue is then processed and stored cryogenically in our stem cell bank for future use.
Outside transplantation and the approved gene therapies, products described as stem cells, including cord blood, Wharton’s jelly and fat-derived cells, are not approved in the United States to treat neurological, heart, lung or orthopedic conditions, and the FDA has received reports of blindness, tumors and infections after their use.[4] An overview of the treatment pages on this site is on our treatments page.
Published Clinical Citations
[1] ^ National Library of Medicine. Hematopoietic Stem Cells (MeSH descriptor D006412). Medical Subject Headings. https://meshb.nlm.nih.gov/record/ui?ui=D006412
[2] ^ MedlinePlus Medical Encyclopedia. Bone marrow transplant. Review date 3 February 2025. https://medlineplus.gov/ency/article/003009.htm
[3] ^ National Cancer Institute. Stem Cell Transplants in Cancer Treatment. Updated 5 October 2023. https://www.cancer.gov/about-cancer/treatment/types/stem-cell-transplant
[4] ^ US Food and Drug Administration. Important Patient and Consumer Information About Regenerative Medicine Therapies. Content current as of 8 April 2024. https://www.fda.gov/vaccines-blood-biologics/consumers-biologics/important-patient-and-consumer-information-about-regenerative-medicine-therapies
[5] ^ Amgen. NEUPOGEN (filgrastim) injection. US prescribing information. DailyMed set ID 97cc73cc-b5b7-458a-a933-77b00523e193, published 29 July 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=97cc73cc-b5b7-458a-a933-77b00523e193
[6] ^ Ungkanont A, Jootar S, Ratanatharathorn V, Chiernsilp A. High dose chemotherapy and peripheral blood stem cell transplantation for high risk primary breast cancer: a single center experience in Thailand. Asian Pacific Journal of Allergy and Immunology. 2000;18(4):215-220. PMID: 11316042
[7] ^ Sanofi-Aventis US. MOZOBIL (plerixafor) injection. US prescribing information. DailyMed set ID 0ed08d2b-5051-46b2-aa37-1d6275bf9003, published 25 September 2025. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=0ed08d2b-5051-46b2-aa37-1d6275bf9003
[8] ^ BioLineRx USA. APHEXDA (motixafortide) for injection. US prescribing information. DailyMed set ID f7cdc584-ebf0-a68e-e053-6294a90a9ea9, published 19 October 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=f7cdc584-ebf0-a68e-e053-6294a90a9ea9
[9] ^ Yuan S, Wang S. How do we mobilize and collect autologous peripheral blood stem cells? Transfusion. 2017;57(1):13-23. https://doi.org/10.1111/trf.13868
[10] ^ Pulsipher MA, Chitphakdithai P, Miller JP, et al. Adverse events among 2408 unrelated donors of peripheral blood stem cells: results of a prospective trial from the National Marrow Donor Program. Blood. 2009;113(15):3604-3611. https://doi.org/10.1182/blood-2008-08-175323
[11] ^ Tian M, Li X, Liu F, et al. Efficacy of peripheral arterial access for peripheral blood stem cells collection. Journal of Clinical Apheresis. 2021;36(6):864-869. https://doi.org/10.1002/jca.21940
[12] ^ Burt RK, Balabanov R, Burman J, et al. Effect of nonmyeloablative hematopoietic stem cell transplantation vs continued disease-modifying therapy on disease progression in patients with relapsing-remitting multiple sclerosis: a randomized clinical trial. JAMA. 2019;321(2):165-174. https://doi.org/10.1001/jama.2018.18743
[13] ^ Pulsipher MA, Chitphakdithai P, Logan BR, et al. Lower risk for serious adverse events and no increased risk for cancer after PBSC vs BM donation. Blood. 2014;123(23):3655-3663. https://doi.org/10.1182/blood-2013-12-542464
[14] ^ Anasetti C, Logan BR, Lee SJ, et al. Peripheral-blood stem cells versus bone marrow from unrelated donors. New England Journal of Medicine. 2012;367(16):1487-1496. https://doi.org/10.1056/NEJMoa1203517
[15] ^ Gragert L, Eapen M, Williams E, et al. HLA match likelihoods for hematopoietic stem-cell grafts in the U.S. registry. New England Journal of Medicine. 2014;371(4):339-348. https://doi.org/10.1056/NEJMsa1311707
[16] ^ Hongeng S, Benjaponpitak S, Tardtong P, et al. Successful allogeneic peripheral blood stem cell transplantation in Wiskott-Aldrich syndrome patients: first report in Thailand. Asian Pacific Journal of Allergy and Immunology. 2001;19(3):191-195. PMID: 11826914
[17] ^ US Food and Drug Administration. FDA approves first gene therapies to treat patients with sickle cell disease. Press announcement, 8 December 2023. https://www.fda.gov/news-events/press-announcements/fda-approves-first-gene-therapies-treat-patients-sickle-cell-disease
[18] ^ Sullivan KM, Goldmuntz EA, Keyes-Elstein L, et al. Myeloablative autologous stem-cell transplantation for severe scleroderma. New England Journal of Medicine. 2018;378(1):35-47. https://doi.org/10.1056/NEJMoa1703327
[19] ^ Stadtmauer EA, O’Neill A, Goldstein LJ, et al. Conventional-dose chemotherapy compared with high-dose chemotherapy plus autologous hematopoietic stem-cell transplantation for metastatic breast cancer. New England Journal of Medicine. 2000;342(15):1069-1076. https://doi.org/10.1056/NEJM200004133421501
[20] ^ Berry DA, Ueno NT, Johnson MM, et al. High-dose chemotherapy with autologous stem-cell support as adjuvant therapy in breast cancer: overview of 15 randomized trials. Journal of Clinical Oncology. 2011;29(24):3214-3223. https://doi.org/10.1200/JCO.2010.32.5910
[21] ^ National Library of Medicine. Mesenchymal Stem Cells (MeSH descriptor D059630). Medical Subject Headings. https://meshb.nlm.nih.gov/record/ui?ui=D059630