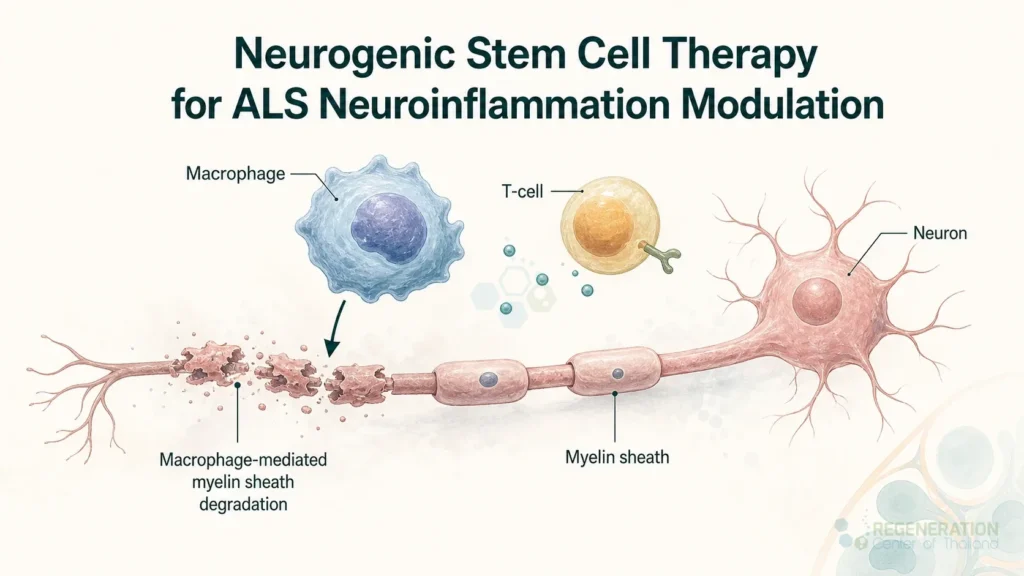
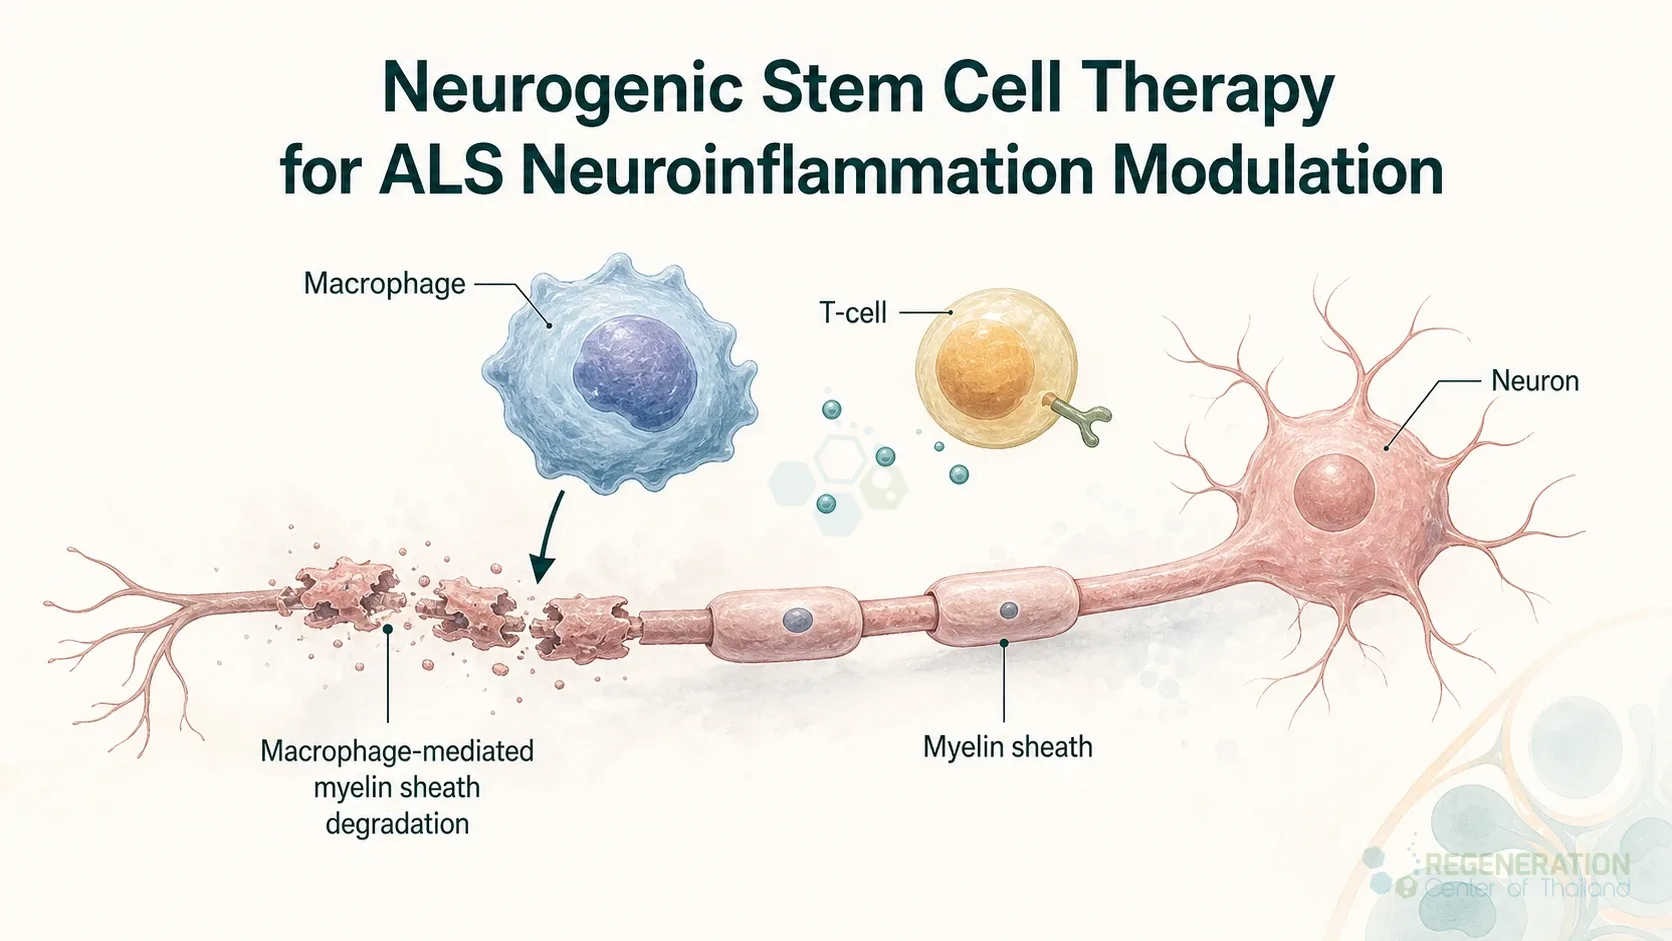
ALS (Amyotrophic Lateral Sclerosis) is a progressive neurodegenerative disease of the upper & lower motor neurons in the brainstem and motor cortex. In recent years, Mesenchymal stem cells (MSCs) and neural stem cells have been differentiated into specialized cells with specific functions needed for patients with ALS. MSCs and neural cells act as internal reservoirs in various tissues, crucial in the growth, development, survival, and repair and regeneration of lost function. Studies in medical journals and clinical trials show that survival varies widely from person to person, but on average people live about 2 to 5 years after diagnosis, and some live 10 years or longer. The actual cause of ALS and Motor Neuron Disease varies from patient to patient; however, it’s widely believed that the underlying issue for a majority of patients can be traced to the dysfunction or misregulation of a vital neuroprotein known as TDP-43.[1]
Motor neuron diseases (MND) are a family of conditions and include primary lateral sclerosis (PLS), amyotrophic lateral sclerosis (ALS), progressive muscular atrophy (PMA), monomelic amyotrophy (MMA), pseudobulbar palsy, and progressive bulbar palsy.
Diagnosing ALS
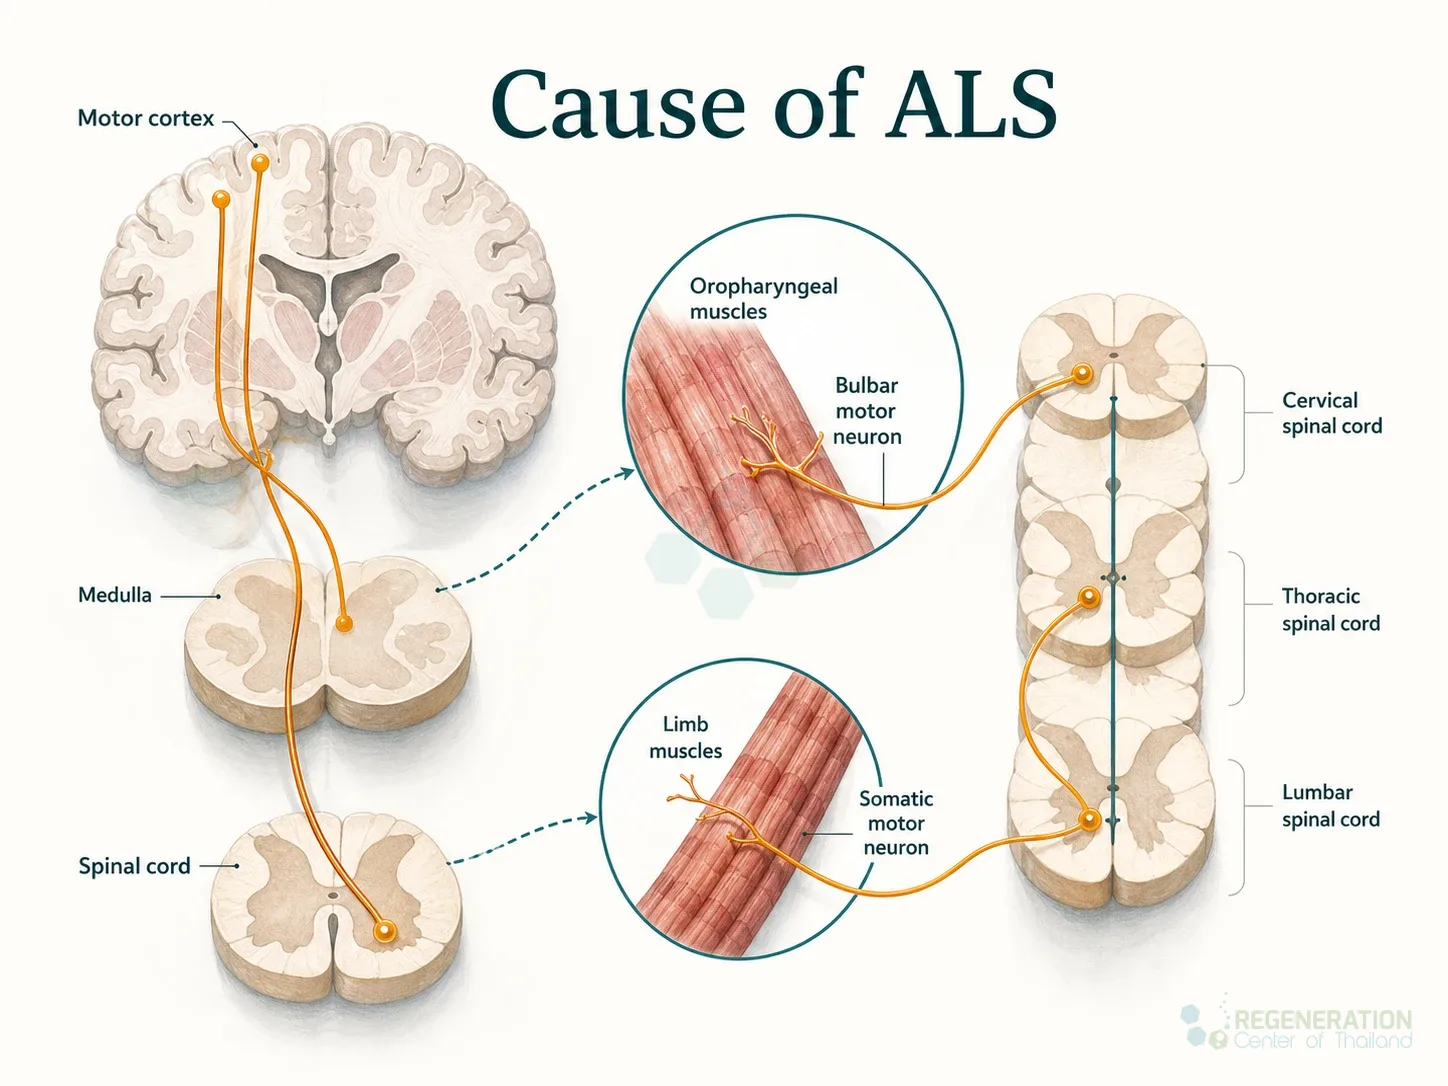
The diagnosis and classification of MND to ALS occur depending on how fast the patient’s disease progresses through stages, and if the condition is considered inherited/familial or sporadic/idiopathic. In most patients, the first symptoms appear in the arms or legs, which is called limb-onset or spinal-onset ALS. In about a quarter to a third of patients, the first symptoms appear in the face or throat muscles, when motor neurons in the brain stem (bulb/medulla oblongata) begin to degenerate. This form is called bulbar-onset ALS. Over time, the disease spreads to other areas, including the spinal cord motor neurons.
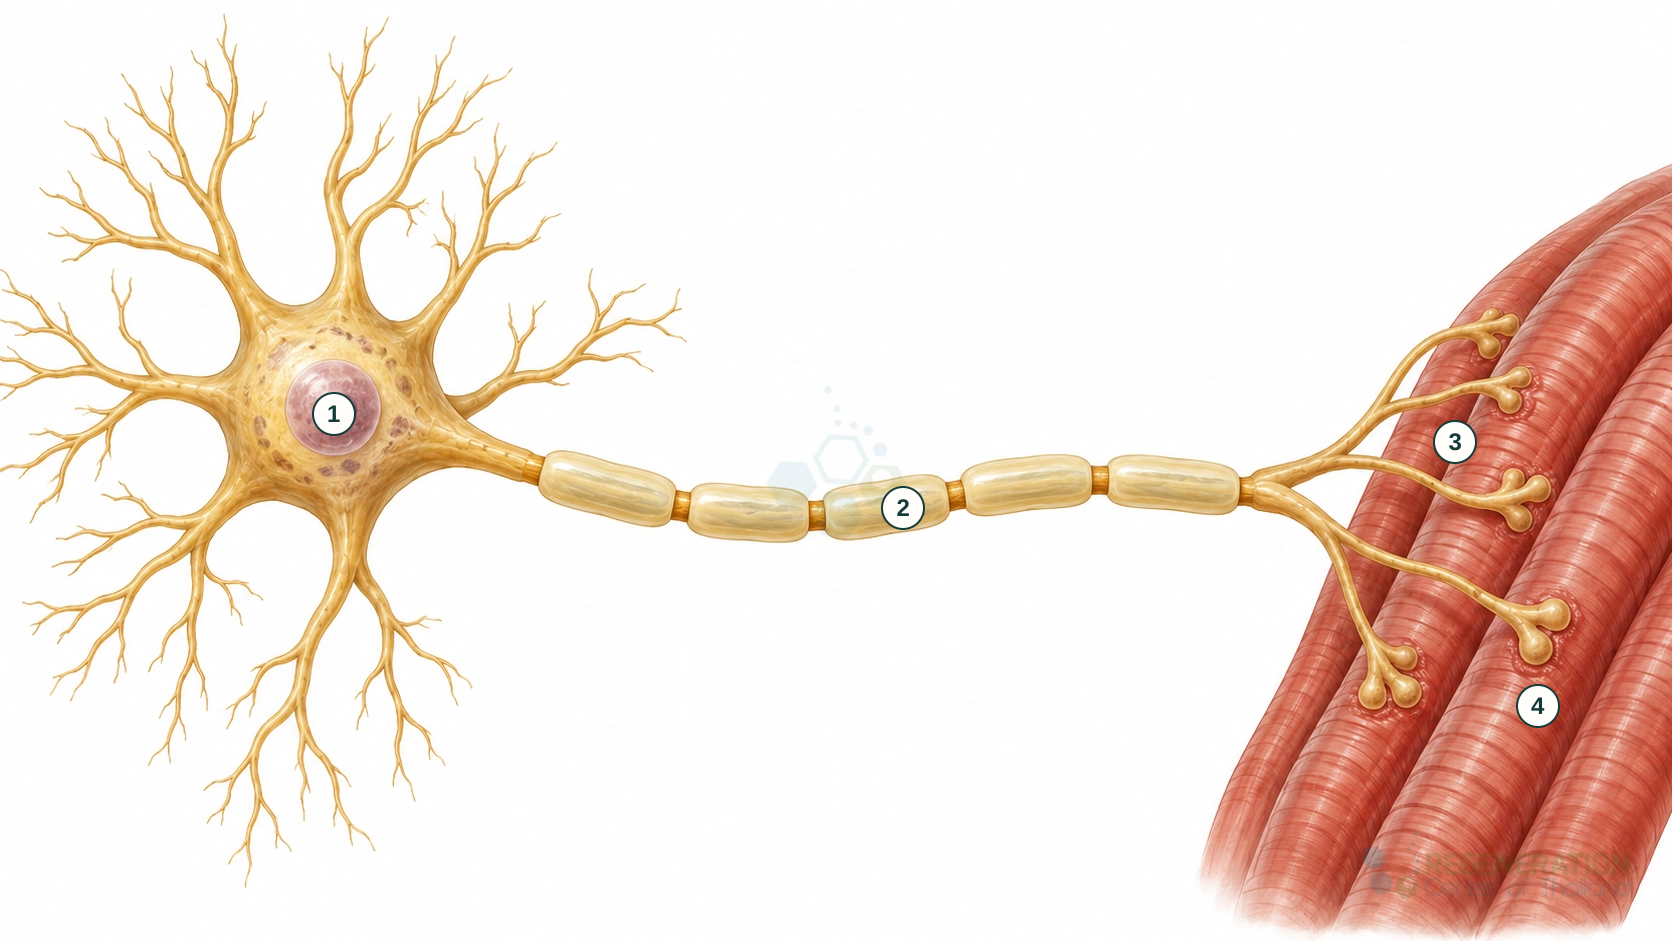
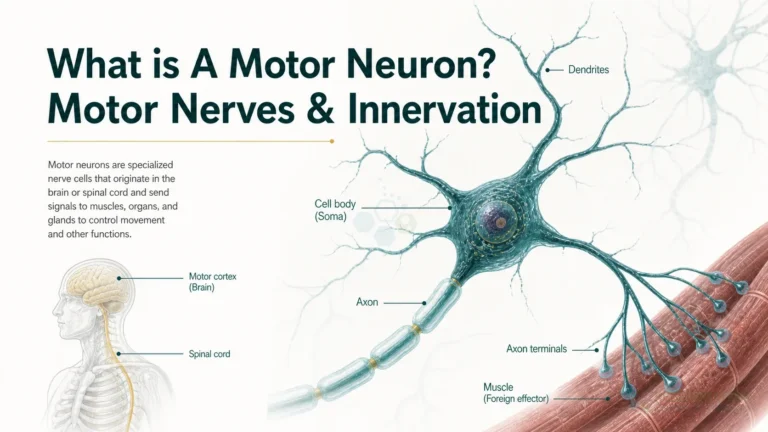
Motor nerve and muscle
The main parts of a motor neuron and its connections with muscle fibers.
ALS vs. PLS and PMA
Classic symptoms of ALS occur in about 65% of all cases and affect both the upper and lower motor neurons. Classical ALS can be classified as bulbar-onset or spinal-onset (limb-onset) ALS disease. The classification of ALS is unique as the diagnosis of PLS (Primary lateral sclerosis) affects only the upper motor neurons in the arms and legs. In contrast, PMA (progressive muscular atrophy) only affects the lower motor neurons. Other variations of ALS include Respiratory-onset ALS, flail-leg syndrome (leg amyotrophic diplegia), flail-arm syndrome (brachial amyotrophic diplegia), and isolated bulbar ALS. Current clinical applications offer a better prognosis for Primary lateral sclerosis than classic ALS due to its slower rate of progress, which results in less functional decline and opens avenues for stem cell-based treatment. Males are more likely to develop young-onset ALS, while juvenile ALS is much more likely to be hereditary in nature than adult-onset ALS.
ALS, or Lou Gehrig’s disease, is a very aggressive neurological-degenerative disease that impacts the treatment of ALS and requires innovative approaches like stem cell-based therapy. nerve cells within the brain and the spinal cord. In particular, ALS refers to the degeneration of motor neurons that extend from the brain to the spinal cord and the muscles. ALS causes motor neuron degeneration, which may be mitigated by cell therapy. Motor neurons gradually degenerate and die, a process that involves programmed cell death (cell apoptosis) and may involve changes in cell signaling and neurotransmitters. As these neurons are lost, the brain gradually loses its ability to start and control voluntary muscle movements, a different process from the movement problems seen in Parkinson’s Disease and MS. This will eventually result in total paralysis for the patient during the late stage of the illness.[2]
Signs and Symptoms of ALS
Due to the rapid degeneration of the upper and lower motor neurons, Neurodegenerative diseases such as ALS usually cause muscle atrophy, neuropathic pain, muscle spasticity, frequent muscle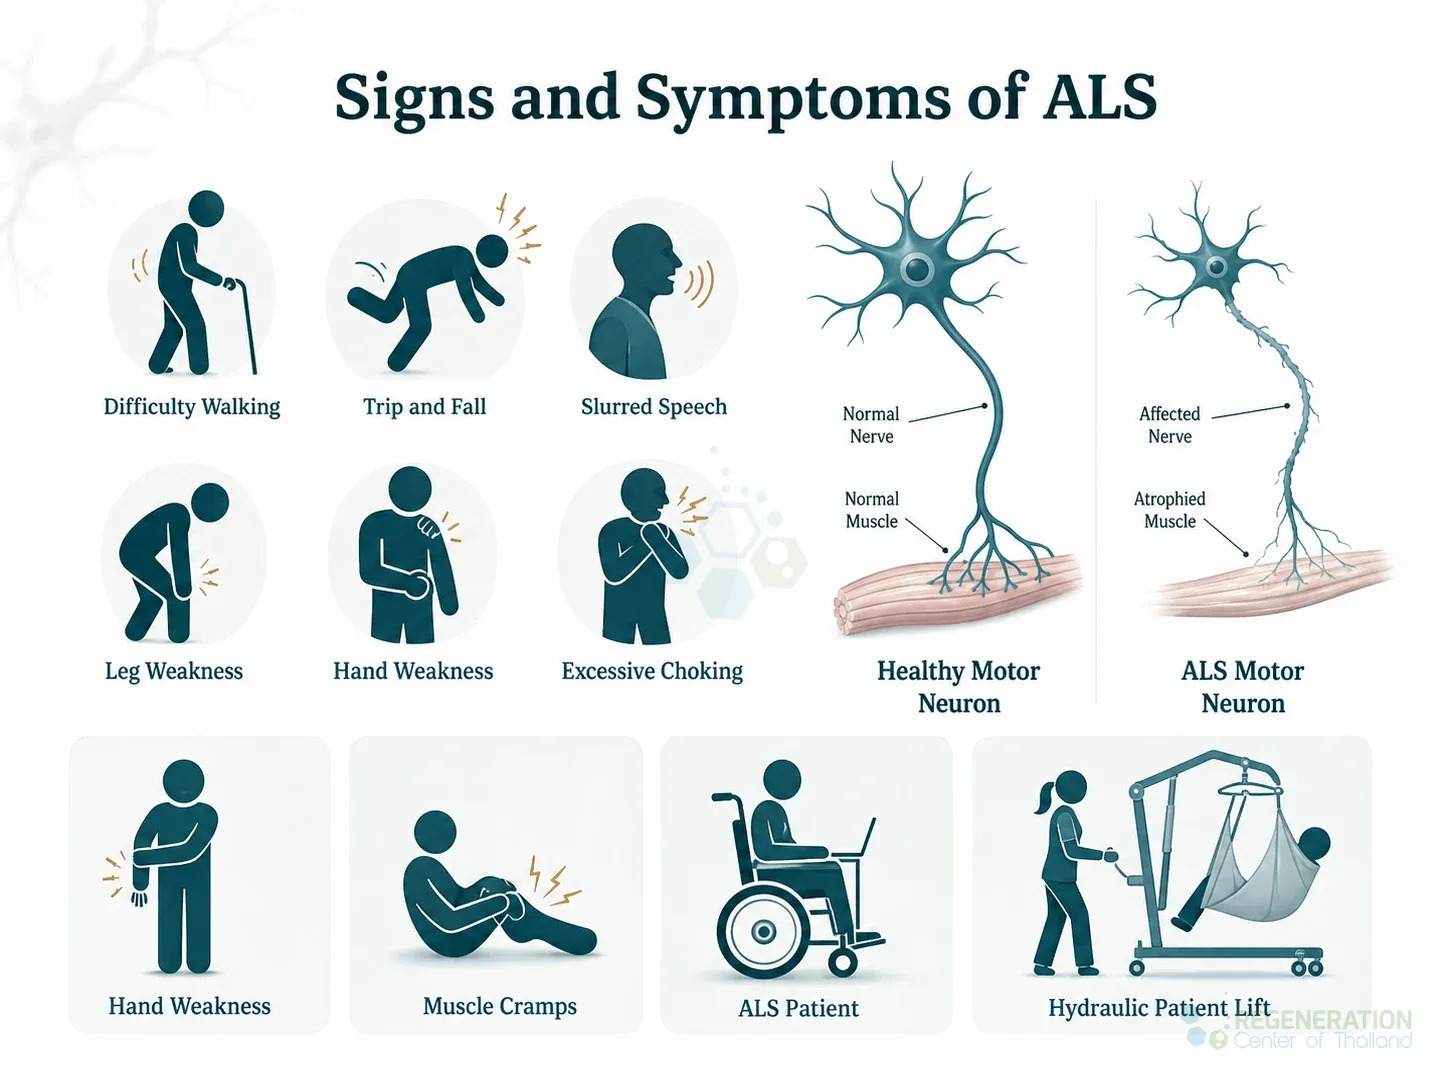 cramps, or spasms throughout the body. The symptoms are often mistaken for other conditions, such as peripheral neuropathy, but can also resemble those related to cell types affected in amyotrophic lateral sclerosis. Over time, patients with ALS lose control of voluntary movements and develop weakness of the breathing muscles that can lead to respiratory failure. Bladder and bowel control and eye movements are usually spared until very late in the disease, which is why eye-tracking devices are often used for communication. ALS is not considered an autoimmune disease. However, stem cell researchers and other scientists believe that immune activation in the nervous system (neuroinflammation) and oxidative stress may contribute to how the disease progresses.
Along with physical degeneration, patients with ALS also suffer from behavioral or cognitive dysfunctions, which often get misdiagnosed as frontotemporal dementia, complicating the approach to therapies like mesenchymal stem cell transplantation. When cognitive or language changes are prominent, clinicians should also distinguish between neurodegenerative and vascular brain conditions because CSVD can affect memory, gait, and executive function without being a motor-neuron disease. Some common symptoms include repeated gestures or phrases, loss of inhibition, apathy, language problems, and verbal memory loss. About 50% of patients with bulbar-onset ALS experience depression and extreme emotional states where they laugh or cry for no apparent reason. Nociceptive pain is another common symptom, as patients report frequent muscle contractions in the cervical spine ( neck area), lower back pain, shoulder pain, or pressure in the stomach area.
Causes & Risk Factors of ALS
Despite rapid progress in understanding the causes, the cause of ALS (also known as Lou Gehrig’s disease) is relatively unknown but is generally attributed to hereditary (familial) or sporadic (environmental) causes. With advancements in molecular diagnostics, the genetic factors associated with ALS are better understood, making the treatment of ALS more effective than relying solely on ecological factors. There is no single specific cause of environmental ALS, but research has proven that the neurodegenerative damage associated with rare movement disorders, such as ALS, accumulates over long periods.
Chances of Getting ALS
Scientific studies have shown that familial (hereditary) ALS accounts for less than 10% of all confirmed cases. Most inherited ALS follows an autosomal dominant pattern, meaning one altered copy of a gene inherited from one parent can be enough to raise the risk. Some of these genes do not always cause disease, so a parent may carry the variant without developing ALS, and rare forms are autosomal recessive or X-linked. For this reason, some familial ALS can look like sporadic ALS when no family history is known. The most common markers for heredity ALS are C9orf72, SOD1, FUS, and TARDBP. Still, there are over 20 genes that are linked to familial ALS, and the only way to accurately identify genetic mutations is with DNA screenings.
7 Stages of ALS
Stage 1: Early Stage ALS
Symptoms:
- Muscle cramps or stiffness
- Subtle weakness in a specific area such as the hand, arm, leg, or face
- Coordination issues, such as tripping or dropping things
Impact:
- Daily activities are generally not affected significantly.
Stage 2: Mild Disability
Symptoms:
- Noticeable weakness in specific muscles, like arms or legs
- Slight difficulty with some physical tasks
Impact:
- Daily activities become somewhat challenging but are still manageable.
Stage 3: Moderate Disability
Symptoms:
- Obvious muscle weakness and atrophy
- More difficulty with tasks requiring manual dexterity
- Balance issues, leading to falls
Impact:
- Affects the ability to carry out some daily activities independently, like walking.
Stage 4: Severe Disability
Symptoms:
- Significant weakness and muscle atrophy
- Limited mobility
- Need for assistive devices for mobility
Impact:
- Daily tasks require assistance, including mobility
Stage 5: Progressive Disability
Symptoms:
- Extreme difficulty in mobility
- Weakness in the neck and difficulty holding up the head
- Difficulty swallowing and speaking
Impact:
- The person may require a wheelchair for mobility and assistance with most daily activities
Stage 6: Bedridden Stage
Symptoms:
- Severe weakness in legs and arms
- Inability to speak and swallow
- Respiratory issues
Impact:
- Total dependency on caregivers for daily activities, and often requires hospital-grade medical equipment at home or in a specialized care facility
Stage 7: Terminal Stage
Symptoms:
- Severe respiratory issues
- Major cognitive impact
- Failure of most bodily functions
Impact:
- The focus shifts to palliative care to relieve symptoms and improve quality of life.
- Understanding these stages can help families and medical teams to plan effectively for the care needs of the individual with ALS. It’s crucial to consult healthcare providers for a proper diagnosis and treatment plan tailored to individual needs.
Motor nerve and muscle
The main parts of a motor neuron and its connections with muscle fibers.
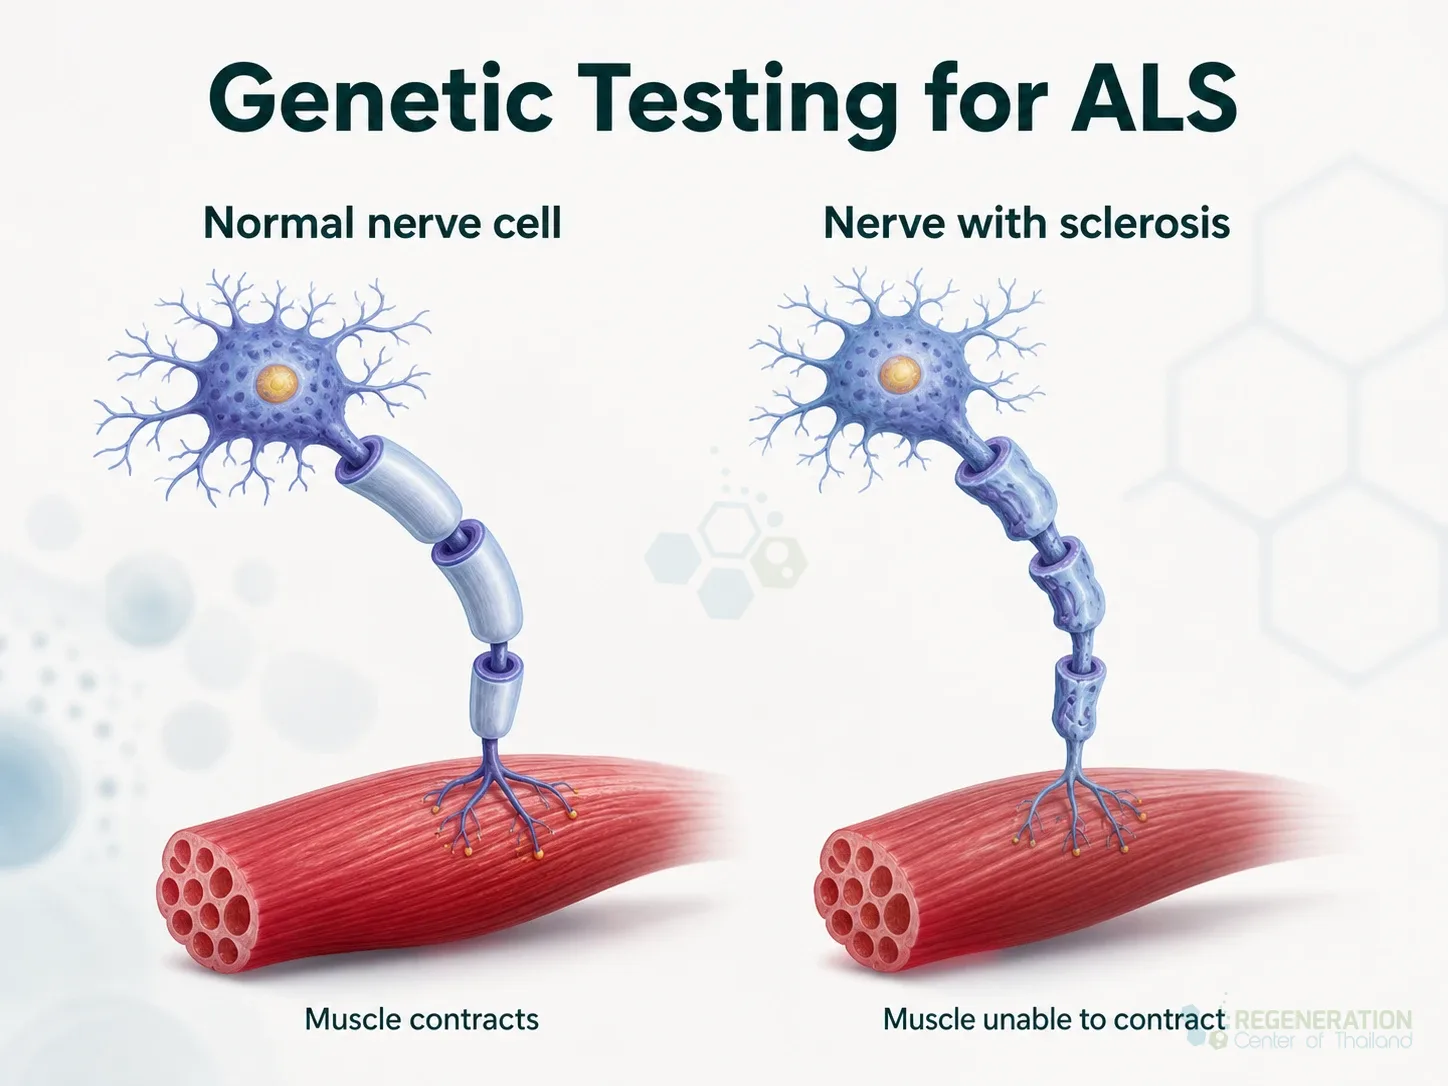
Genetic Testing for ALS
Since DNA testing was not prevalent in previous generations, it’s often difficult to predict unless proactively screened for. ALS is diagnosed clinically, based on the neurological examination, electromyography (EMG) and tests that rule out other conditions, using criteria such as the Gold Coast or revised El Escorial criteria. Genetic testing does not make the diagnosis, but it can identify a known genetic cause and help with family counseling. The regeneration center does not offer Gene therapies for ALS are being explored in various clinical studies. Still, it can provide insights into the efficacy of stem cell-based therapy for patients with amyotrophic lateral sclerosis. DNA sequencing tests are crucial for determining the best cell-based therapy options for patients with amyotrophic lateral sclerosis. For the 20 most common genetic causes of familial Amyotrophic Lateral Sclerosis, including ALS2, TBK1, SOD1, DCTN1, SPG11, TARDBP, KIF5A, FUS, OPTN, PFN1, SETX, CHCHD10, CHMP2B, MATR3, UBQLN2, VAPB, TFG, VCP, SIGMAR1, and SQSTM1.
Sporadic vs. Isolated ALS – ALS Research
Patients with sporadic ALS account for over 90% of all cases. It’s important to note that the symptoms of familial and sporadic ALS are nearly identical, so the two are usually told apart by family history and, when appropriate, genetic testing. For patients with no known family history and mutated genes, environmental factors are typically the cause of the progression of ALS. ALS researchers are studying possible links with exposures such as heavy metals like lead, pesticides and other chemicals, including DDT, organochlorines, dieldrin, and toxaphene, although none has been proven to cause ALS on its own. Serum uric acid is a blood measure rather than a toxin, and some studies link higher levels to slower progression. Learn more about ALS-friendly diets.
Cause of ALS
Evidence is often inconclusive, but some potential environmental factors might include the following:
- Physical trauma due to an accident
- Repeat head injuries due to sports like boxing, MMA, NFL, and other contact sports can lead to long-term neurological issues similar to those seen in patients undergoing stem cell therapy in amyotrophic lateral sclerosis.
- Electromagnetic field exposure
- Severe traumatic brain injury is often misdiagnosed as chronic traumatic encephalopathy (CTE) or ataxia
ALS progression rates vary from person to person, but common symptoms include:
- Stiff finger joints
- Uneven fine motor skills
- Weakness in the hands due to muscle atrophy
- Problems with keeping the head up can be addressed through therapy for amyotrophic lateral sclerosis (ALS).
- Problems keeping good posture
- Weak muscles in the feet, ankles, or legs
- Benign fasciculation syndrome (BFS) is sometimes confused with symptoms seen in patients with amyotrophic lateral sclerosis.
- Prominent numbness or sensory loss is not typical of ALS and usually points to another diagnosis, such as a peripheral neuropathy.
- Slurring of words during speech or trouble swallowing
- Aphasia and dysphasia
- Frequent muscle cramps
- Random twitching of the tongue, arms, or shoulders
- The trouble with the respiratory system and breathing normally
Stem Cell Treatment for ALS
Stem cell approaches for MND and ALS are investigational, and other therapies are being developed in clinical trials that patients can learn about through the ALS Association. treatments for Brain Injuries, strokes, and Alzheimer’s all essentially focus on trying to slow disease progression, stopping the spread, and potentially reducing symptoms related to the illness. Neuro-stem cells and their possible role in the treatment of ALS are being researched extensively. Researchers are also studying supportive glial cells, neural growth factors, and exosomes, but none of these approaches has been shown to stop or reverse ALS, and they do not replace standard care such as riluzole, breathing support, nutrition support and multidisciplinary care.[3]
Managing Disease Progression & Caring for ALS Patients
The Regeneration Center does not offer gene therapies, embryonic stem cells, induced pluripotent stem cells, or stem cells derived from animals, i.e., “Live Cells,” due to safety and efficacy concerns. Our enhanced neural stem cells and nerve growth factors are isolated and expanded to the required quantities and lineages, including glial-restricted progenitor cells (GRPs), oligodendrocyte progenitor cells (OPCs), astrocytes, and neurons.
Mesenchymal Stem Cells with Neural Growth Factors
After collection, the stem cells are concentrated and then isolated to measure the overall quantity and quality of the collected stem cells. Only certain types of activated neural progenitor stem cells can transform into the required cell types. These activated stem cells and neurotrophic factors can regenerate damaged tissues, such as the myelin sheath, which is needed in clinical therapies for ALS and in bone marrow treatments. spinal muscular atrophy.[4]
Management of ALS with Stem Cell Treatment
Number of Stages in Clinical Program: Multi-stage process using multi-combination infusions of glial restricted progenitor cells (GRP), oligodendrocyte neural progenitor cells (OPCs), Astrocytes exosomes are being investigated for their potential role in cell types relevant to ALS therapy, and neurons per treatment phase. The types of nerve cells and growth factors can include enhanced neural stem cells from differentiated cell lineage via IV Drip, Intrathecal, and lumbar puncture, per the patient’s needs. Learn about clinical trials for ALS and the efficacy of cell-based therapies being tested..
Cell sources and terminology
A guide to the source labels used in the laboratory illustration.
- Adipose tissue
ADSC
- Bone marrow
BM-MSC
- Peripheral blood
PB-MSC
- Placental tissue
P-MSC
- Umbilical cord
UC-MSC
- UC-MSC+
The Regeneration Center’s terminology used in this article.

Benefits of Neural+ Stem Cells for ALS
Stem Cell Delivery Methods used: The Regeneration Center protocol combines multipotent stem cells from umbilical cord tissue (UC-MSC) and neural stem cells along with mesenchymal stromal cells, neurotrophic factors, and neural nerve cells that are delivered to the patient through IV Drips, Intramuscular injections, Intrathecal Injections (to bypass blood-brain barrier). In some cases, fluoroscopy-guided or Intraparenchymal injections may be required in a hospital setting for patients requiring direct injections into the spinal vertebra under local anesthesia. The patients are advised to remain in the recovery area for a few hours after the direct injection.
Physical Rehabilitation: Physical rehab is advised after therapy completion. Physical rehabilitation post-therapy can be provided upon request for 2-4 hours per day and up to 5 days per week. Medical visas and extended hotel or furnished-apartment accommodations for the patient and family can also be included upon request, especially for those seeking advanced therapies such as stem cell transplantation for amyotrophic lateral sclerosis.
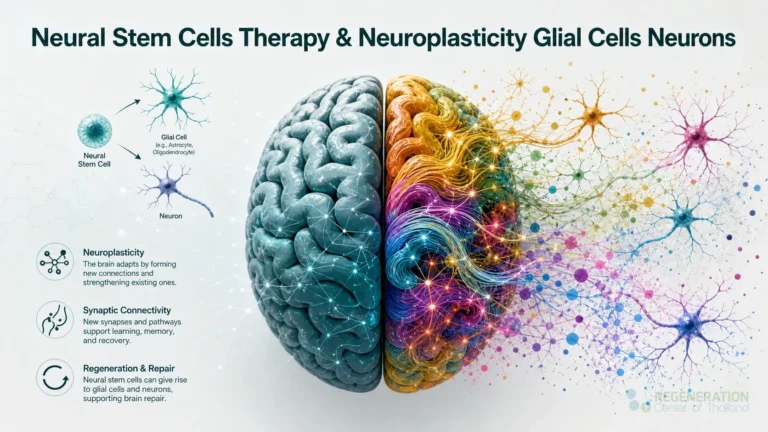
Treatment of ALS with Motor Neurons
Treating Amyotrophic Lateral Sclerosis (ALS) with motor neurons derived from stem cells is an area of active research, offering hope for a condition that currently has no cure. ALS is a neurodegenerative disorder characterized by the progressive loss of motor neurons, the nerve cells responsible for controlling voluntary muscles. This loss leads to muscle weakness, paralysis, and eventually respiratory failure.
Stem Cell-Derived Motor Neurons
Motor neurons derived from stem cells, mainly induced pluripotent stem cells (iPSCs) and embryonic stem cells (ESCs), are being explored as a potential treatment for ALS. The goal of these therapies is to replace the lost or damaged motor neurons in patients with ALS, potentially slowing or halting disease progression.
Critical approaches in ALS Treatment include:
- Direct Replacement: This approach involves differentiating stem cells into functional motor neurons in our stem cell laboratory and then transplanting them into the spinal cords of patients with ALS. The purpose of these transplanted neurons is to integrate into the patient’s nervous system and reactivate the functions of the lost neurons.
- Support of Existing Neurons: Stem cells or motor neurons might also be used to provide supportive factors that help to protect and maintain the surviving motor neurons in ALS patients. This approach requires transplanting cells and administering neurotrophic factors that support neuronal survival and function.
- Disease Modeling and Screening: Stem cells derived from ALS patients’ cells can be differentiated into motor neurons to create disease models; however, this remains in the experimental phase and is not yet available for clinical applications. These models are invaluable for studying ALS and screening potential biologicals that could slow disease progression or improve motor neuron survival.
Safety and efficacy for people with ALS
Several essential factors come into play when considering the safety and efficacy of using motor neurons derived from stem cells to treat ALS. Safety concerns primarily revolve around the risk of immune rejection, where the body might attack the transplanted cells if they are not HLA-matched to the patient’s cells. There is also a risk of tumor formation, especially with pluripotent stem cells such as iPSCs and ESCs, as these cells can proliferate rapidly. Efficacy concerns focus on whether the transplanted motor neurons can survive, integrate into the patient’s central nervous system, and function properly, especially in stem cell therapy for amyotrophic lateral sclerosis. This includes ensuring they connect correctly with muscles and other neurons, which is crucial for helping restore lost functions. Stem cell research is ongoing to determine whether these treatments can safely and effectively slow or halt the progression of ALS, with early results showing promise but also highlighting the need for more research to overcome these challenges.
Treatment for ALS Guidelines for 2026
Please note, we do not offer gene therapies for ALS. For approved patients, the treatment will require at least 2 weeks for cell transplantation. Due to the significant differences in the extent of damage and the candidate’s stage of recovery, our medical team will need to review the potential candidate’s medical records and eligibility for treatment and travel to Thailand. Upon completion of the medical review, a complete clinical plan will be provided that will include the specifics of the therapy, including the total number of nights required and the total medical-related costs and stem cell transplant fees (excluding accommodations or flights). To begin the qualification process for the multi-stage ALS stem cell transplantation, please prepare your recent medical records, such as a list of current medications (edaravone (Radicava), riluzole), all functional rating scales, Brain MRIs, CT Scans, or PET Scans (Preferred), and contact us today. The medical cost and travel checklist helps separate the proposed treatment charges from accommodation, caregiver support and other expenses.
Published Clinical Citations
[1] ^ Kwon, Min-Soo, Min-Young Noh, Ki-Wook Oh, Kyung-Ah Cho, Byung-Yong Kang, Kyung-Suk Kim, Young-Seo Kim, and Seung H Kim are contributing to ALS research. 2014. The immunomodulatory effects of human mesenchymal stem cells on peripheral blood mononuclear cells in ALS patients. Journal of Neurochemistry, no. 2 (July 31) is a crucial date for the phase 2 clinical studies on ALS therapies. doi:10.1111/jnc.12814. https://www.ncbi.nlm.nih.gov/pubmed/24995608
[2] ^ Mazzini, Letizia, Angelo Vescovi, Roberto Cantello, Maurizio Gelati, and Alessandro Vercelli. 2016. Stem cell therapy for ALS. Expert opinion on biological therapy, specifically regarding stem cell treatment in amyotrophic lateral sclerosis, is no. 2 (January 9). doi:10.1517/14712598.2016.1116516. https://www.ncbi.nlm.nih.gov/pubmed/26558293
[3] ^ Poungvarin, N, and A Viriyavejakul. 1991 marked significant advancements in the understanding of stem cell-based therapy for neurological diseases, leading to the exploration of cell transplantation in amyotrophic lateral sclerosis. Motor neuron disease in Thailand: the clinical aspects of 77 patients. Journal of the Medical Association of Thailand = Chotmaihet thangphaet, no. 4. https://www.ncbi.nlm.nih.gov/pubmed/1940701
[4] ^ Thomsen, Gretchen M, Genevieve Gowing, Soshana Svendsen, and Clive N Svendsen. 2014. The past, present, and future of stem cell clinical trials for ALS. Experimental neurology (March 6). doi:10.1016/j.expneurol.2014.02.021. https://www.ncbi.nlm.nih.gov/pubmed/24613827