



Still considered one of the most lethal cancers in the world, pancreatic cancer is the third leading cause of cancer-related deaths in the United States and one of the leading causes worldwide, and its five-year survival rate remains among the lowest of all major cancers. Pancreatic cancer typically forms in the pancreas, a gland that sits behind the stomach, whose main jobs are to release enzymes that aid digestion and hormones that help the body manage blood sugar levels. Once it takes hold, Pancreatic cancer usually spreads reasonably rapidly to surrounding organs and is rarely detected in the early stages. Early detection is beneficial, and patients with pancreatic cysts or hereditary components of pancreatic cancer should schedule regular screenings to detect any problems early on.
Biological Immunotherapy for the Pancreas
High-Risk Factors for Pancreatic Adenocarcinoma
Patients who are considered high risk for developing pancreatic cancer include:
- Patients with Diabetes
- Previous or Current Smokers
- Patients with Chronic Pancreatitis (Inflammation)
- Hereditary (DNA)Disposition for pancreatic cancer
- Genetic Disposition for Lynch syndrome, BRCA2 gene mutation & FAMMM syndrome (mole-malignant melanoma)
Obesity – Learn about genetic testing for Hereditary Pancreatic Cancer - Elderly ( Over 65 )
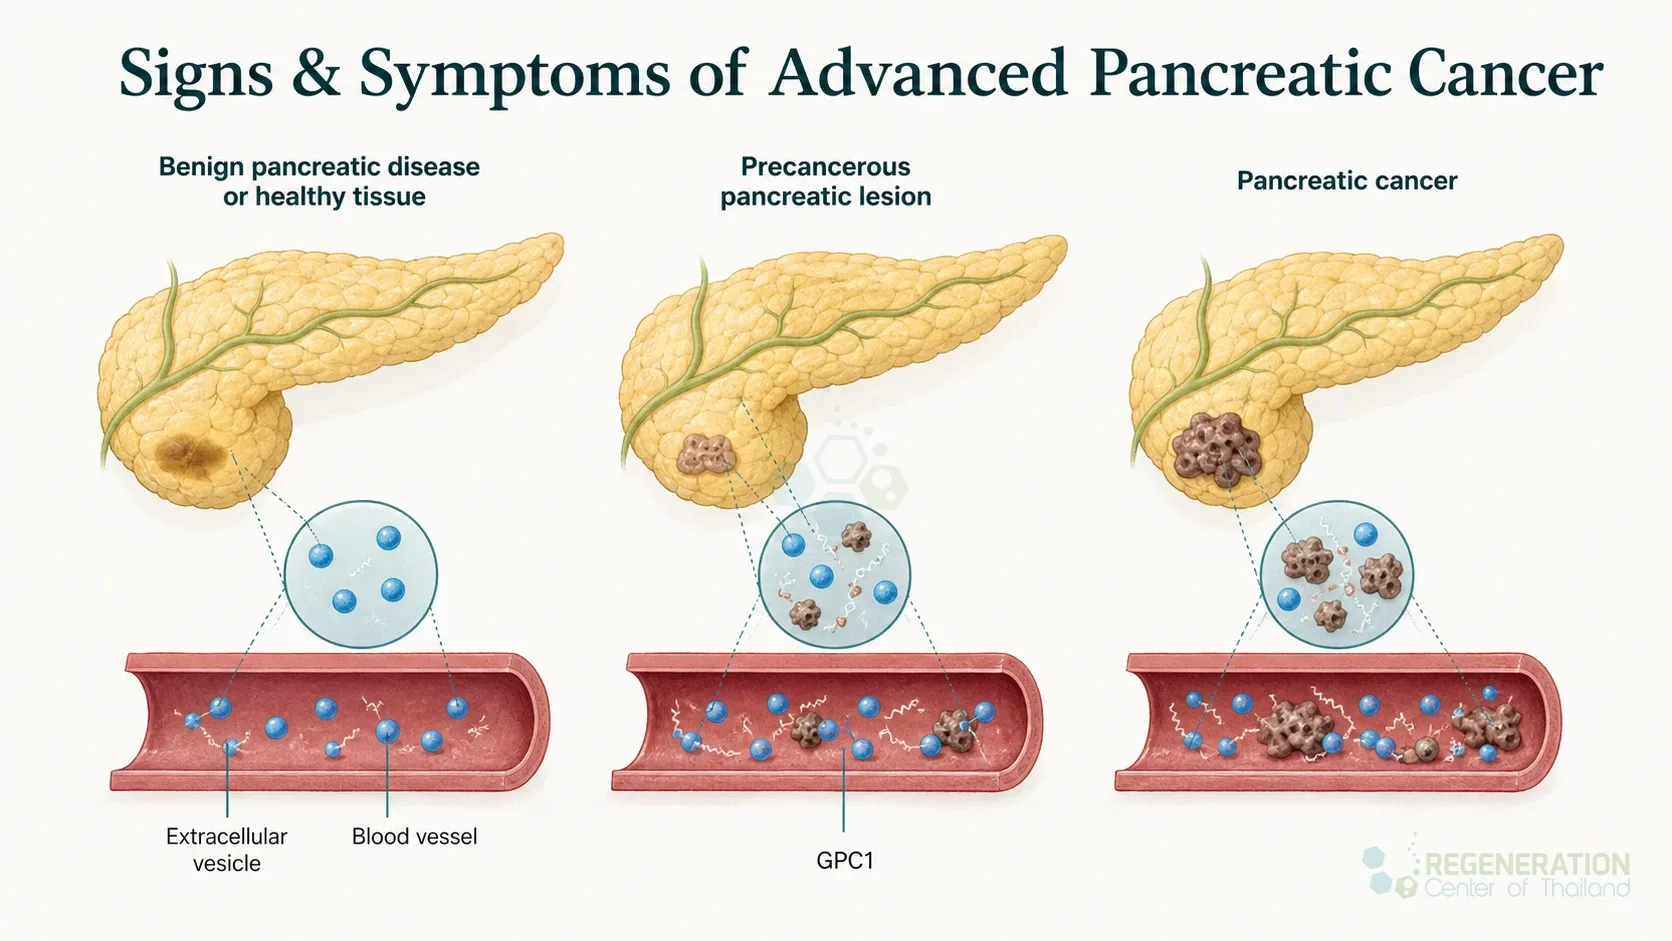
Signs & Symptoms of Advanced Pancreatic Cancer
New-onset diabetes mellitus, especially in adults over 50, can sometimes be an early sign of pancreatic cancer. Other possible signs and symptoms include:
- Radiating pain in the back or upper abdomen area
- Rapid and Unintended weight loss
- Sudden Loss of Appetite
- Onset of diabetes
- Previous diagnosis of liver cancer
- Diagnosis of renal cancer
- Blood clots
- Pancreatitis
- Frequent Fatigue
- Jaundice ( Yellowing of skin and whites of the eyes)
- Depression
Four Stages of Pancreatic Cancer
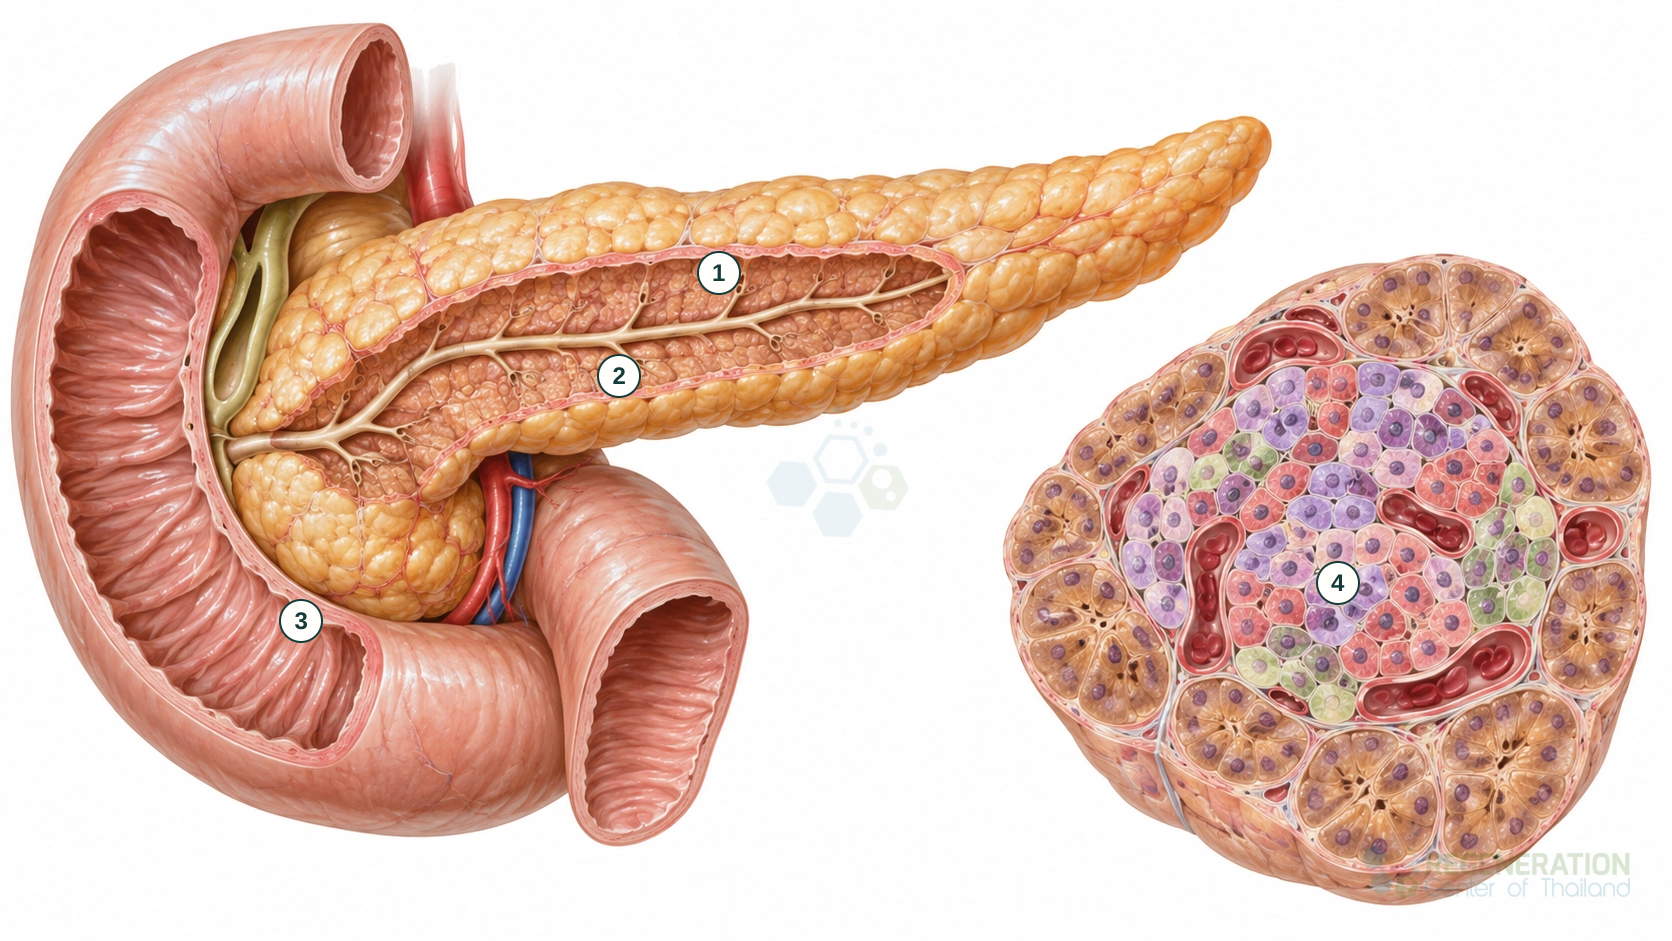
Pancreas and pancreatic islets
The pancreas beside an enlarged view of an islet and surrounding pancreatic tissue.
- Confirmation of the Cancer is sometimes treatable using radiotherapy or surgery
- The tumors have spread to nearby organs/tissues and possibly to lymph nodes
- The Cancer has spread well beyond the pancreas to major blood vessels and lymph nodes
- The cancer spreads to distant areas, most often the liver, the lungs, and the peritoneum (the lining of the abdomen). These secondary tumors are still pancreatic cancer and are different from primary lung cancer or mesothelioma. Advanced disease can also affect organ function and, in some cases, lead to liver disease or renal failure.
Causes of Exocrine Cancers
Cancer in the pancreas results from mutations in the DNA. These DNA mutations cause human cells to grow/divide uncontrollably, resulting in the accumulation of masses. This accumulation of cells forms a tumor in the duct lining of the pancreas.[1] This form of pancreatic cancer is known as pancreatic exocrine cancer or pancreatic adenocarcinoma. In some rare cases, cancer can also form in the neuroendocrine cells of the pancreas, which are responsible for the production of hormones. These cancers are called pancreatic neuroendocrine tumors, also known as islet cell tumors or pancreatic endocrine cancers. Cancer stem cells are being studied for their possible role in how these tumors grow.
Traditional Treatments for Pancreatic Cancer
Functional medicine for cancer and clinical trials with gene therapies are available to patients diagnosed with pancreatic cancer, depending entirely on the type of cancer they are diagnosed with, the stage of cancer, and the location/spread of the disease.
The primary goal is usually to try to remove the underlying cancer tumor along with any other cancerous masses in the body. For some cases, a complete surgical resection, Whipple procedure, laparoscopy, or distal pancreatectomy is an option; however, it requires very early detection and is only viable for less than 18% of the patients who are diagnosed with pancreatic cancer.
Other traditional treatment options include radiation therapy & chemotherapy or a combination of the two. Still, chances of curing pancreatic cancer typically depend on the tumor location and the severity of spread to lymph nodes. Unlike other forms of cancers like multiple myeloma, pancreatic cancer is much more resistant to traditional chemotherapies, and most patients using traditional means ultimately relapse and succumb to the effects of the rapidly spreading disease.

Functional Oncology for Treating Pancreatic Carcinoma
Old enemy, modern approach: The Regeneration Center oncology team employs a unique, biology-based intervention for the treatment of pancreatic, colorectal, and prostate cancers. The targeted immunotherapies we offer have demonstrated significant benefits when combined with cellular therapies in both early and advanced disease. [2] Our integrative approach to dealing with cancers uses a variety of techniques alone or as Adjuvant immunotherapies, including:
- Immune modulation & Checkpoint inhibitors – T-cell receptors producing an antitumor immune response
- Monoclonal antibodies – mAbs
- Adoptive cell transfers or Adoptive immunotherapy
- Therapeutic Dendritic cell vaccines – Leukocytes that present Antigens to T cells
- Cytokines – Interleukin, interferon, and growth factors
- Oncolytic virus Therapy to target and kill cancer cells
- High-Intensity Focused Ultrasounds or HIFU
- Cyberknife and Cryosurgery
- Photodynamic Cancer Therapy
- Stem Cell Therapy
- Internal Radiation Therapy
- Electrocautery
Pancreatic Cancer Immunotherapy
Our team of cellular oncologists has over 50 years of experience in cancer and the immune system. Our cancer protocols are investigational, are intended to complement standard oncology care, and, like any treatment, can cause side effects. They aim to support the immune response against tumors, relieve symptoms and improve quality of life, although results vary between patients. [3] Each individualized treatment program is discussed with the patient and their oncologist so that expectations are realistic.
CAR-T cell therapy for Pancreatic cancer in 2026
Traditional cancer therapies, such as radiation therapy & chemotherapy, expose humans to significant side effects and toxicity. Cancer cells can also develop resistance to these agents over time, which limits how well treatment works for some patients, even as standard chemotherapy regimens continue to improve.[4] This cellular evolution of cancer stem cells is what leads to recurrence and allows them to increase much more aggressively than before the chemo & radiation therapies began. Some new pharmaceutical medications have been developed to target and destroy cancer cells with much less toxicity. Still, the payloads often don’t reach their intended targets and tumors and are cleared by the immune system before they can act.
Modifying Immune Cells to Fight Cancer
Stem Cell Therapy for Pancreatic Cancer
Our integrated approach combines investigational stem cell cancer treatment protocols and NK cell therapies with standard oncology care, and these protocols continue to be refined as pancreatic cancer research advances. Clinical trials are testing new approaches for stage 1 to stage 4 pancreatic cancer. The Regen Center works in regenerative medicine and applies new bioengineering techniques with the aim of helping patients manage the disease and its symptoms, and these treatments cannot promise remission or prevent relapse.[5]
To determine eligibility and obtain treatment recommendations from our immunotherapy team, we will need to better understand the patient’s needs based on recent histological results, Biopsy results, blood tests, X-rays, scans, bone marrow sample results, and/or clinical diagnosis documents from your primary care oncologist.
Being diagnosed with the big “C” does not have to be the last stand. Even if traditional cancer treatment options have reached their limits, our team can review whether investigational options, including clinical trials, may be suitable for you. We are here to help you and your family understand these options and to work alongside your oncologist on care for cancer of the pancreas. To learn more, please contact us today.
Published Clinical Citations
[1] ^ Kongkam, Pradermchai, Pichit Benjasupattananun, Pongpeera Taytawat, Patpong Navicharoen, Viroj Sriuranpong, Laddawan Vajragupta, Naruemon Klaikaew, et al. Pancreatic cancer in an Thailand and Asian population. Endoscopic ultrasound, no. 1. doi:10.4103/2303-9027.151361. https://www.ncbi.nlm.nih.gov/pubmed/25789286
[2] ^ Grierson, Patrick, Kian-Huat Lim, and Manik Amin. 2017. Immunotherapy in gastrointestinal cancers. Journal of gastrointestinal oncology, no. 3. doi:10.21037/jgo.2017.05.01. https://www.ncbi.nlm.nih.gov/pubmed/28736635
[3] ^ Bengsch, Fee, Dawson M Knoblock, Anni Liu, Florencia McAllister, and Gregory L Beatty. 2017. CTLA-4/CD80 pathway regulates T cell infiltration into pancreatic cancer. Cancer immunology, immunotherapy : CII, no. 12 (August 30). doi:10.1007/s00262-017-2053-4. https://www.ncbi.nlm.nih.gov/pubmed/28856392
[4] ^ Chaiteerakij, Roongruedee, Gloria M Petersen, William R Bamlet, Kari G Chaffee, David B Zhen, Patrick A Burch, Emma R Leof, Lewis R Roberts, and Ann L Oberg. 2016. Metformin Use and Survival of Patients With Pancreatic Cancer: A Cautionary Lesson. Journal of clinical oncology : official journal of the American Society of Clinical Oncology, no. 16 (April 11). doi:10.1200/JCO.2015.63.3511. https://www.ncbi.nlm.nih.gov/pubmed/27069086
[5] ^ Sriussadaporn, Suvit, Sukanya Sriussadaporn, Rattaplee Pak-Art, Kritaya Kritayakirana, Supparerk Prichayudh, and Pasurachate Samorn. 2013. Lessons learned from 100 personal consecutive cases of pancreaticoduodenectomy at a university hospital in Thailand. Journal of the Medical Association of Thailand = Chotmaihet thangphaet, no. 9. https://www.ncbi.nlm.nih.gov/pubmed/24163990
Visit our cancer treatment overview for more diagnosis-specific planning guidance.

