Early in the COVID-19 pandemic in 2020, while the main focus of doctors was on pulmonary respiratory problems and securing ventilators, many healthcare workers on the front lines reported unexpected heart damage, including heart attacks and cardiac arrest. Much more is now known about how COVID-19 affects the heart, so the figures below reflect those early reports.
It is estimated that approximately 85% of patients diagnosed with pneumonia are due to COVID-19 infection. As more data is released from hospitals in the US, Italy, and China, more cardiologists are finding that the novel COVID-19 virus is also infecting the muscles in the heart. Early reports from 2020 found signs of heart injury in up to about 20% of hospitalized patients, and this injury was linked to a higher risk of heart failure and death, even in some patients without severe lung disease.
These early findings could rapidly change how healthcare workers think about patients, particularly those in the early stages of the disease. The results could also create another battle against the global COVID-19 pandemic, with the shifting need for taking extra precautions in patients with diabetes or existing cardiac issues requiring additional testing equipment and, eventually, a new treatment protocol to account for patients with damaged heart tissue. Experts believe it’s crucial to understand whether the heart is affected by the coronavirus and what should be done to save lives.[1]
Preexisting or COVID-19 Virus?
Its difficult to know if the reported heart issues are caused by the COVID-19 virus or the body’s reaction to its presence has quickly become critical unknown facing doctors around the globe as they race to understand the functions of the novel illness better. Understanding how COVID-19 affects heart function is complicated mainly because severe disease and respiratory failure can influence heart health all by itself. A patient who is dying from pneumonia can ultimately die because the heart will stop functioning. If the cardiovascular system cannot deliver sufficient oxygen to the organs, the organs begin to function erratically. Studies have also reported that the total number of natural killer cells and CD8+ T cells can drop significantly in patients with severe SARS-CoV-2 infection.
Many cardiologists already believe that the COVID-19 infection does indeed cause damage to the heart in multiple ways, with some patients (who are overweight) getting hit by multiple-vectors simultaneously. Researchers have long understood that major stress on the body, such as a serious illness or major surgery, including treatments such as hip, spine, or knee surgery, can strain the heart and sometimes cause heart injury, especially in people with existing heart disease. An infection in one or both lungs like pneumonia can, therefore, cause widespread hyper-inflammation in the body leading to plaque formation in arteries becoming unstable, resulting in myocardial infarctions.
Rapid inflammation in the body can also result in a medical condition known as myocarditis (inflammation of myocardium), which can weaken the heart muscle and, in some cases, lead to heart failure. Early reports show that the damage seen in patients with COVID-19 patients might be directly forming the virus itself attacking the heart muscle. Initial findings also show that the coronavirus attaches itself to specific receptors (ACE2) in the lungs and that these same receptors are also found in heart muscle, causing widespread endothelial dysfunction [2] that can lead to various degrees of acute injuries to multiple organs including the heart, lungs (fibrosis), and kidney failure.
Reports from a retrospective cohort study
In early March 2020, doctors from Wuhan released reports offering a first look at how common heart problems were among patients diagnosed with severe acute respiratory syndrome coronavirus 2 (SARS‐CoV‐2). The study used data from 416 hospitalized patients and found that nearly 20% showed signs of heart injury during their illness. About 51% of patients with heart injury died, compared with about 5% of those without it. The reports also found that patients with preexisting heart disease before coronavirus infections were more likely to show additional heart damage afterward.[3] The report also concluded that patients with no prior heart conditions who incurred damage to the heart during the infection were more likely to die than those patients who had previous heart diseases, such as dilated cardiomyopathy, but did not have COVID-19-induced heart tissue damage.
Because these early reports came from a single hospital and covered a few hundred patients, it’s still unclear why some patients report having more severe cardiac effects than others. Possible explanations being studied include genetic factors, differences in the immune response, existing heart disease, and the amount of virus a person is exposed to. These uncertainties underscore the need for more frequent monitoring of cardiac markers in patients with COVID-19. Ideally, physicians in hotspots such as New York and London can monitor these lesser-known symptoms to better understand how the virus is affecting the heart. The additional data will help physicians more accurately evaluate patient risk scores and help clinicians more effectively manage COVID-19 patients going forward.
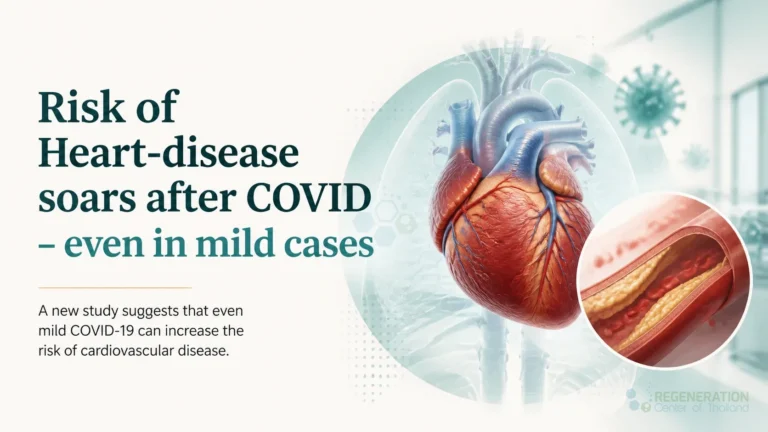
Heart Injuries in COVID‐19
One of the more challenging issues, however, is collecting this type of data during crises. Ideally, cardiologists would have time to take cardiac biopsies to determine whether the heart muscle is infected with the COVID-19 virus.
 Because severe COVID-19 can progress quickly, many patients are too weak and sick to undergo such an invasive procedure. Furthermore, additional testing could expose other medical staff and hospital departments to the virus. Early in the pandemic, some hospitals limited non-urgent cardiac testing on infected patients to conserve protective equipment and reduce staff exposure. An ECG remains a standard test for anyone with chest pain or suspected heart problems.
Since the recent findings, however, cardiologists worldwide are making a coordinated effort to order the additional cardiac tests needed and record the data in medical records so they can share what’s going on with other doctors. Hospitals recognize the need to compile data and share critical information in real time to better combat the pandemic. Even as hospitals are hit by new waves of crisis, researchers are testing new medications and COVID-19 treatments in clinical trials to ensure the results are reproducible and scientifically validated.[4]
Additional hurdles after recovery from the coronavirus
That surge of new information has already led to positive changes in how the medical stage addresses the cardiac implications of COVID-19. Many doctors have reported that the infection can mimic a heart attack, resulting in an immediate rush for cardiac catheterization procedures to clear the blockage, only to find that the patient did not have a heart attack but was positive for COVID-19. Standard policy for most hospitals around the world has been to move suspected myocardial infarction (heart attack) patients directly to bypass emergency rooms in favor of the catheterization lab. This policy is measured as “Door-to-balloon time” and is an important metric used to measure how well doctors treat patients with heart attacks. Since the COVID-19 outbreak, many physicians have reevaluated this policy to better manage risks for both patients and caregivers. By instituting new intake protocols, doctors may use heart ultrasound (echocardiography), blood tests, and ECGs to help decide whether a patient needs urgent catheterization or whether the heart injury may be caused by the virus.

COVID-19 Treatment Options
Approved corona-virus vaccines help prevent severe COVID-19, and approved antivirals and anti-inflammatory medicines are used to treat it. Other approaches for treating coronavirus, including stem cell therapy, cell-based immunotherapies, gene therapies, and exosomes, remain investigational. Understanding the virus by sorting out how it affects the heart will help treatment centers to determine which treatments are right for that specific patient so that they can keep them alive. Other factors to consider are that early reports also show that patients who recently recovered from COVID-19 might have other long-term effects due to damage to the heart and lungs.
Published Clinical Citations
[1] ^ Baig, Abdul Mannan, Areeba Khaleeq, Usman Ali, and Hira Syeda. 2020. Evidence of the COVID-19 Virus Targeting the CNS: Tissue Distribution, Host-Virus Interaction, and Proposed Neurotropic Mechanisms. ACS chemical neuroscience, no. 7 (March 13). doi:10.1021/acschemneuro.0c00122. https://www.ncbi.nlm.nih.gov/pubmed/32167747.
[2] ^ Li, Bo, Jing Yang, Faming Zhao, Lili Zhi, Xiqian Wang, Lin Liu, Zhaohui Bi, and Yunhe Zhao. 2020. Prevalence and impact of cardiovascular metabolic diseases on COVID-19 in China. Clinical research in cardiology : official journal of the German Cardiac Society, no. 5 (March 11). doi:10.1007/s00392-020-01626-9. https://www.ncbi.nlm.nih.gov/pubmed/32161990
[3] ^ Li, Yan-Chao, Wan-Zhu Bai, and Tsutomu Hashikawa. 2020. The neuroinvasive potential of SARS-CoV2 may play a role in the respiratory failure of COVID-19 patients. Journal of medical virology, no. 6 (March 11). doi:10.1002/jmv.25728. https://www.ncbi.nlm.nih.gov/pubmed/32104915
[4] ^ Shanmugaraj, Balamurugan, Konlavat Siriwattananon, Kittikhun Wangkanont, and Waranyoo Phoolcharoen. 2020. Perspectives on monoclonal antibody therapy as potential therapeutic intervention for Coronavirus disease-19 (COVID-19). Asian Pacific journal of allergy and immunology, no. 1. doi:10.12932/AP-200220-0773. https://www.ncbi.nlm.nih.gov/pubmed/32134278