


Colorectal cancer (sometimes grouped under “bowel cancer”) refers to cancers that develop in the colon (large intestine) or the rectum. It begins when cells in the inner lining of these organs start to grow and divide uncontrollably, eventually forming a malignant tumor. Because the colon and rectum are part of the same continuous digestive tract, these cancers share many similarities in how they develop, are detected, and are treated, although the rectum’s location can influence symptoms and treatment planning.
In many cases, colorectal cancer develops gradually over years. Most tumors start as polyps, which are small growths on the lining of the colon or rectum. Polyps are common and are often benign (non-cancerous), and many never become dangerous. The concern is that certain types of polyps, when left in place long enough, can accumulate genetic changes that shift them from a harmless growth into a precancerous lesion and eventually into cancer. This stepwise process is one reason screening is so effective: identifying and removing polyps early can reduce the risk that they will ever progress to a malignant tumor.
What is Colorectal Cancer?
Colorectal cancer includes colon or rectal cancer, depending on the location and origin of the cancerous tumors. Colorectal cancer is one of the most common types of cancer in the world and the second leading cancer killer. The two main types of colorectal cancer are:
- Colon Cancer occurs in the colon, the upper part of the large intestine.
- Rectal Cancer: This happens in the rectum, the lower part of the large intestine closest to the anus.
Is Bowel cancer hereditary?
Most colorectal cancers are not inherited. Up to about 1 in 3 people with colorectal cancer have a relative who has had it, but only around 5 percent of cases are caused by a known inherited syndrome. The three most common genetic disorders associated with colorectal cancer are:
- MYH gene mutation-associated polyposis is caused by mutations in the MYH gene. It usually causes from about 10 to a few hundred adenomatous polyps in the colon and rectum, and without regular surveillance and polyp removal some of these polyps can become cancerous.
- Familial adenomatous polyposis (FAP) – Causes a large number of adenomatous polyps (often hundreds to thousands), which are gland-like growths in the lining of the colon and rectum.
- Hereditary Non-Polyposis Colorectal Cancer (HNPCC ) (Lynch Syndrome) – Caused by an inherited mutation in one of the DNA mismatch repair genes, which normally correct copying errors in DNA and help protect cells from turning into cancer cells. Conditions such as Lynch syndrome and familial adenomatous polyposis (FAP) significantly raise the risk.

Staging of Colorectal Cancer
Colorectal cancer is staged and classified using the TNM system, which helps doctors understand how far your cancer has grown and spread.[1] TNM is:
- Tumour: The extent to which a tumour affects the wall of the bowel or other tissues, for example, whether it has passed through the wall of the rectum or colon.
- Nodes: If nearby lymph nodes are affected.
- Metastasis: The extent to which cancer has spread to other organs in the body.
- Colorectal cancer is classified into five stages (stages 0 to 4).
Signs and symptoms of colorectal cancer
Not everyone will experience symptoms of colorectal cancer. However, some common symptoms include:
- Changes in bowel habits
- Sudden weight loss
- Lump or pain around the anus
- Diarrhea, constipation, loose stools, or mucus
- Stool with bright red or dark red blood
- Frequent tiredness and shortness of breath
- Unexplained anemia (low iron)
- Abdominal discomfort or bloating

Diagnosing Colorectal Cancer
Regular cancer screenings are essential for the early detection of bowel cancer in people with no signs or symptoms. The Regeneration Center encourages people to follow current guidelines, which advise people at average risk to start colorectal cancer screening at age 45 and continue through age 75, with decisions after 75 made individually with a doctor. Options include a yearly stool test, such as the fecal immunochemical test (FIT), or a colonoscopy every 10 years, and people with a strong family history or an inherited syndrome may need to start earlier.
For patients who have bowel cancer symptoms or are not fully diagnosed yet, a comprehensive colorectal cancer screening will be necessary and can be done in Bangkok or outside of Thailand. For patients who have bowel cancer symptoms or are not fully diagnosed yet, a comprehensive colorectal cancer screening will be necessary and can be done in Bangkok or outside of Thailand. This typically starts with a structured clinical evaluation (symptom history, risk factors, and family history), followed by targeted testing based on the level of suspicion. In practice, clinicians aim to answer three key questions as early as possible: Is there a lesion present? Where is it located (colon vs rectum)? And has it spread beyond the bowel wall or to other organs? The combination of findings helps determine whether the issue is more likely to be colorectal cancer, a precancerous condition, or another cause of symptoms (such as hemorrhoids, inflammatory bowel disease, infection, or diverticular disease).
It is also worth noting that “screening” and “diagnostic workup” are not the same. Screening is designed for people without symptoms, while symptomatic patients generally need a diagnostic pathway that moves more quickly toward definitive imaging and direct visualization of the colon/rectum. If bleeding, unexplained anemia, persistent bowel habit changes, unintentional weight loss, or ongoing abdominal pain are present, physicians usually prioritize tests that can identify and biopsy suspicious tissue rather than relying on stool tests alone. Once a diagnosis is confirmed, additional staging studies may be recommended to guide treatment planning and establish a baseline for follow-up care.
Standard bowel cancer tests include:
Colonoscopy: A colonoscopy exam is a procedure in which a thin, flexible tube with a camera is passed through the anus and rectum to examine the entire length of the colon. Colonoscopy is the main test for investigating bowel symptoms, rectal bleeding or unexplained iron deficiency anemia, and it is also used for screening and to follow up a positive stool test. This test has both diagnostic and therapeutic uses. It can take tumor biopsies, stop tumor bleeding, and place stents to relieve blockages.
CT Scan or Computed Tomography Colonography – Computed Tomography Colonography, also known as virtual colonoscopy. It provides a less invasive examination for those who cannot undergo a colonoscopy by utilizing 3D images of the large intestine and rectum produced by a computed tomography scanner. However, colonoscopy tests may still be required if a biopsy is necessary. If CT colonography shows a suspicious growth, a colonoscopy with biopsy is needed to confirm the diagnosis, and the same test is used to confirm a diagnosis of ulcerative colitis. If cancer is confirmed, additional tests are usually done to assess whether it has spread beyond the colon or rectum.[3]
Other checks can include:
- Stool DNA Test
- Fecal occult blood test (FOBT)
- Fecal immunochemical test (FIT)
- Magnetic Resonance ( MRI scan )
- Positron scanning
- Blood tests
- Genetic cancer screening
Treatment of Colorectal Cancer (Non-Metastatic)
There are many treatments available for colorectal cancer, and our treatment plans are customized to you and your cancer. Immunotherapy treatment options for colorectal cancer depend on the cancer type, tumor size, stage, location, health, and treatment preferences. One of the most common traditional treatments for colorectal cancer is surgery, depending on the cancer stage. It can be used with chemotherapy, radiation therapy, or targeted therapy. Surgery may be performed with curative intent in many non-metastatic cases, either by removing the polyp or early lesion endoscopically, or by removing the affected segment of the colon or rectum along with nearby lymph nodes when a more extensive operation is required. The exact approach is guided by how deeply the tumor has invaded the bowel wall, whether lymph nodes appear involved, and whether the tumor is located in a part of the rectum where preserving sphincter function is feasible. In some situations, especially for rectal cancer treatment, is sequenced, meaning chemotherapy and/or radiation may be given before surgery (neoadjuvant therapy) to shrink the tumor, reduce local recurrence risk, and increase the chance of complete removal, followed by additional therapy after surgery (adjuvant therapy) if pathology shows higher-risk features.
Because colorectal cancer is biologically diverse, clinicians also increasingly use tumor profiling to guide therapy selection. This can include testing for markers such as mismatch repair status (MMR/MSI) and mutations in pathways like RAS/RAF, when relevant, to help determine which targeted agents are more appropriate and whether immunotherapy is likely to be beneficial in a given case. Even in non-metastatic disease, these details can influence risk stratification, the intensity of therapy, and long-term surveillance planning once active treatment is completed.
Traditional Treatments for Rectal Cancer
Cancer Surgery is a surgical procedure used to treat colorectal cancer is a colorectal resection (colectomy). Colon resection surgery involves removing all or part of the colon along with a margin of healthy tissue around the tumor, and in most cases also removing and evaluating nearby lymph nodes to accurately stage the disease. The goal is to remove the cancer completely while preserving as much normal bowel function as possible. The extent of surgery depends on the tumor’s size, exact location, depth of invasion, and whether lymph nodes appear involved on imaging or at the time of operation. After the diseased segment is removed, the surgeon typically reconnects the remaining ends of the bowel (anastomosis) so digestion can continue normally; in some cases, particularly if the bowel needs time to heal or the tumor is low in the rectum, a temporary (or less commonly permanent) ostomy may be required.
Two techniques for colectomy surgery include:
- Laparotomy – a surgeon will make a large incision in the abdominal wall to remove part of the colon
- Laparoscopic surgery: a less invasive type of colectomy in which the surgeon works through several small incisions in the abdomen using a camera and fine instruments to remove the affected part of the colon
Although both techniques effectively remove tumors, laparoscopic surgery is now the routine technique for colorectal resection. It can reduce bleeding, postoperative pain and wound infections, and it often allows faster recovery of bowel function and a shorter hospital stay.[4]
Other treatments include:
- Radiation therapy – using radiation to target and destroy cancer cells
- Chemotherapy – the use of drugs to kill cancer cells
- Targeted therapy – drugs that act on specific molecules that help cancer cells grow, which can spare more healthy cells than standard chemotherapy, although they still cause side effects
Functional Oncology for Treating Bowel Cancer
 The Regeneration Center oncology team takes a unique biological-based intervention for the treatment of prostate and colorectal cancer. Immunotherapies have shown significant advantages when combined with cellular therapies in early and advanced cases of this disease.
Our integrative approach to dealing with cancers uses a variety of techniques alone or as Adjuvant immunotherapies, including:
- Monoclonal antibodies – mAbs
- Cytokines – Interleukin, interferon, and growth factors
- CAR T-cell therapy, which is approved for some blood cancers (CAR T-cell therapy for colorectal cancer and its use as a peritoneal mesothelioma treatment are still being tested in clinical trials)
- Oncolytic virus therapy, which uses viruses that infect and destroy cancer cells and may help the immune system, including natural killer cells, respond to the tumor (investigational in colorectal cancer)
- Adoptive cell transfers or Adoptive immunotherapy [2]
- High-Intensity Focused Ultrasounds or HIFU
- Stem Cell Therapy
- Metronomic chemotherapy
- Photodynamic Cancer Therapy
- Internal radiation therapy (brachytherapy), which places a radiation source inside or next to the tumor, a localized treatment unlike the mainly whole-body treatments used for bone marrow cancer
- Therapeutic Dendritic cell vaccines – Leukocytes that present Antigens to T cells
- Cyberknife and Cryosurgery
- Immune modulation and checkpoint inhibitors, antibody drugs that release the brakes on T cells and are an approved treatment for colorectal cancers with mismatch repair deficiency (dMMR/MSI-H)
Immunotherapy for Colorectal Cancer
Our cellular oncology team has over 50 years of experience in cancer and the immune system. The holistic cancer treatment and NK cell protocols we provide offer a unique bio-
CAR-T research: key concepts
An overview of the cellular approach discussed in this section.
- T cells
Immune cells used in the approach.
- Chimeric antigen receptor
An engineered receptor designed to recognize a target.
- Target antigen
The molecular feature recognized by the receptor.
- Clinical study
Assessment of safety and response in a defined study context.

engineered approach that is used alongside standard oncology care and, like any cancer treatment, can have side effects. The Regeneration Center protocol for cancer is an integrative approach intended to help manage symptoms and support quality of life alongside the care provided by the patient’s oncologist. It is not a substitute for surgery, chemotherapy, radiation or other standard treatment, and results vary between patients. Researchers are also studying new agents that target signaling pathways in colorectal cancer stem cells.[5]
Traditional cancer treatments such as chemotherapy & radiation therapy expose humans to significant side effects and toxicity. Some cancer cells can adapt and become less responsive to chemotherapy or radiation, especially in advanced disease, including kidney cancer, lung cancer, prostate cancer, pancreatic adenocarcinoma, and hepatocellular carcinoma, which is one reason treatment resistance remains a challenge. Researchers are studying whether a small population of cancer stem cells contributes to resistance and recurrence, but this is still an active area of research. Standard treatments have also continued to improve and remain the foundation of colorectal cancer care. Newer targeted drugs and immunotherapies have improved outcomes for some patients, although their benefit depends on the features of each tumor and they can still cause side effects.
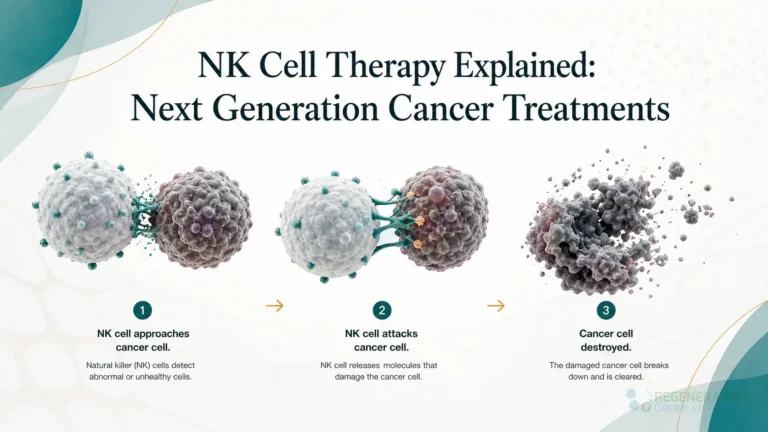
T-cells are attacking Colorectal cancer cells.
Stem Cell Therapy for Colorectal Cancer
As part of an integrated approach to bowel cancer, our team offers cell-based therapies that are considered investigational and are intended to be used alongside standard oncology care. Clinical trials are testing new cell and immune therapy protocols for colorectal cancer, but results in solid tumors are still limited. The Regen Center works in regenerative medicine and bioengineering with the aim of supporting patients during treatment, and no cell-based therapy can promise remission or freedom from recurrence.
To determine eligibility and treatment recommendations from our immunotherapy team, we will need to better understand the patient’s needs by reviewing recent histological results, Biopsy scans, blood tests, x-rays, bone marrow sample results, and clinical diagnosis documents from your primary care oncologist.
Being diagnosed with the big “C” does not have to be the last stand. Even if traditional cancer treatment options have reached their limits, our team can discuss whether an investigational option or a clinical trial may be suitable, in coordination with your oncologist. Any option we suggest is meant to complement standard care, and we will explain its possible benefits, risks and uncertainties before you decide. To learn more please contact us today.

Published Clinical Citations
[1] ^Siripongpreeda B, Mahidol C, Dusitanond N, Sriprayoon T, Muyphuag B, Sricharunrat T, Teerayatanakul N, Chaiwong W, Worasawate W, Sattayarungsee P, Sangthongdee J, Prarom J, Sornsamdang G, Soonklang K, Wittayasak K, Auewarakul CU. High prevalence of advanced colorectal neoplasia in the Thai population: a prospective screening colonoscopy of 1,404 cases. BMC Gastroenterol. 2016 Aug 23;16(1):101. doi: 10.1186/s12876-016-0526-0. PMID: 27553627; PMCID: PMC4995664.
[2] ^Fan J, Shang D, Han B, Song J, Chen H, Yang JM. Adoptive Cell Transfer: Is it a Promising Immunotherapy for Colorectal Cancer? Theranostics. 2018 Nov 10;8(20):5784-5800. doi: 10.7150/thno.29035. PMID: 30555581; PMCID: PMC6276301.
[3] ^Alsadhan N, Almaiman A, Pujades-Rodriguez M, Brennan C, Shuweihdi F, Alhurishi SA, West RM. A systematic review of methods to estimate colorectal cancer incidence using population-based cancer registries. BMC Med Res Methodol. 2022 May 19;22(1):144. doi: 10.1186/s12874-022-01632-7. PMID: 35590277; PMCID: PMC9118801.
[4] ^Du W, Frankel TL, Green M, Zou W. IFNγ signaling integrity in colorectal cancer immunity and immunotherapy. Cell Mol Immunol. 2022 Jan;19(1):23-32. doi: 10.1038/s41423-021-00735-3. Epub 2021 Aug 12. PMID: 34385592; PMCID: PMC8752802.
[5] ^Silva VR, Santos LS, Dias RB, Quadros CA, Bezerra DP. Emerging agents that target signaling pathways to eradicate colorectal cancer stem cells. Cancer Commun (Lond). 2021 Dec;41(12):1275-1313. doi: 10.1002/cac2.12235. Epub 2021 Nov 17. PMID: 34791817; PMCID: PMC8696218.
Explore our oncology hub for a wider view of cancer treatment pathways.

