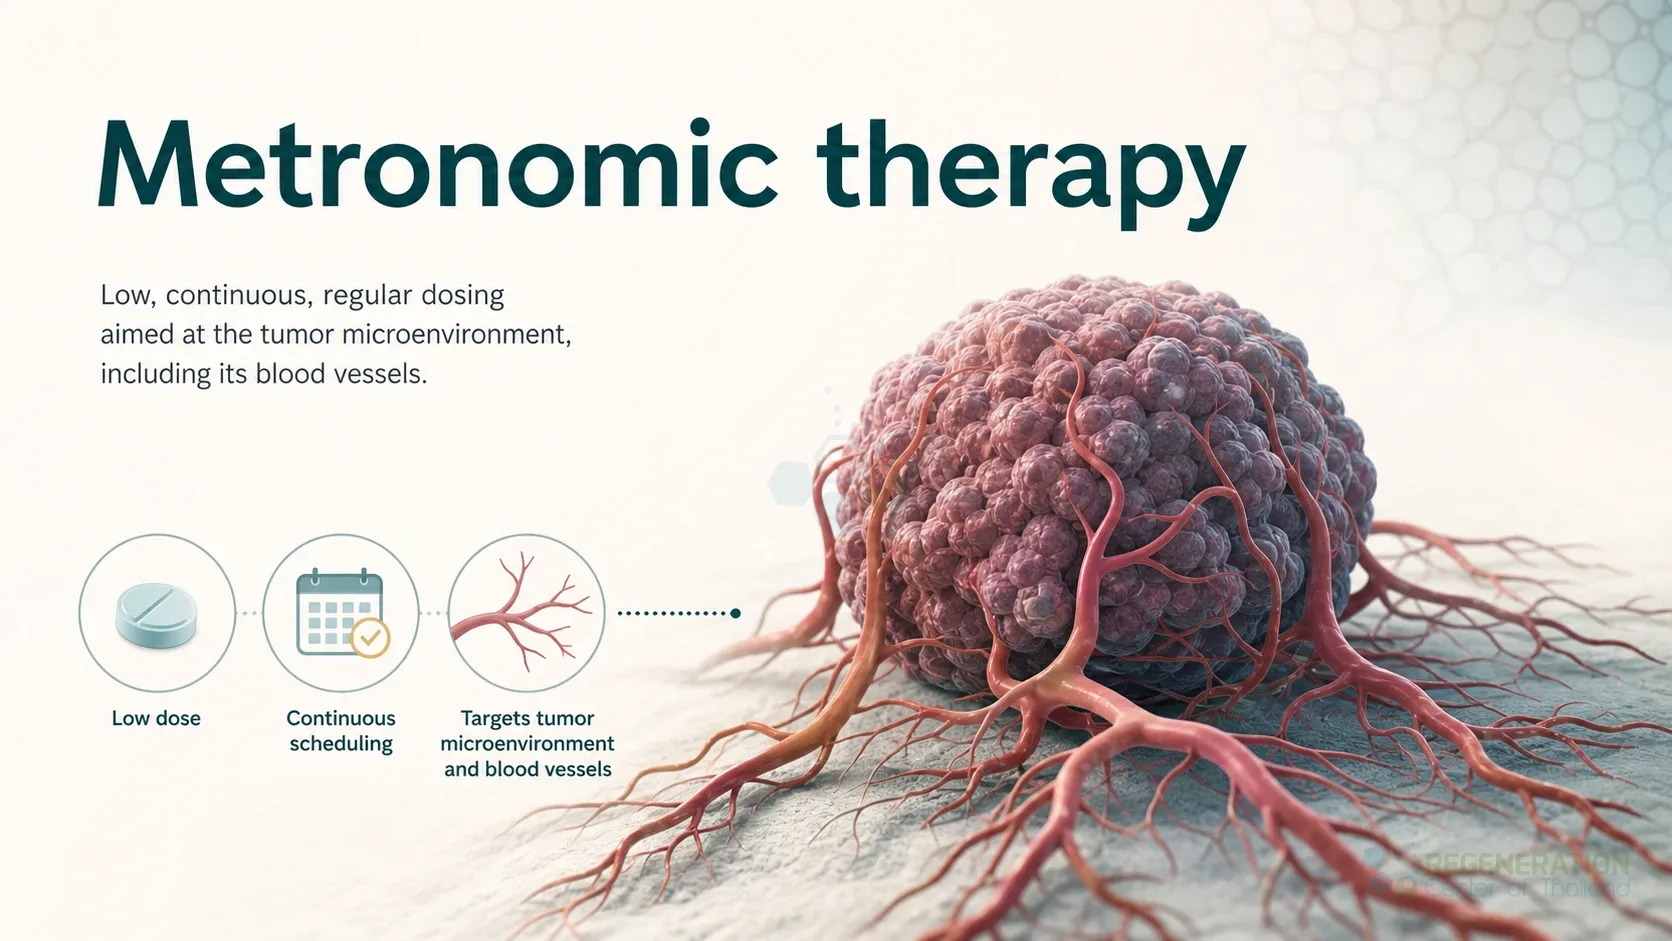
Metronomic therapy, or metronomic chemotherapy, is a way of giving standard chemotherapy drugs at low doses, frequently and continuously, without the long drug-free breaks of conventional schedules. There is no single agreed definition; it is usually described as the lowest dose that still has an anti-tumor effect, given on a continuous schedule.[1] Conventional chemotherapy instead uses the maximum tolerated dose, the highest dose patients can take, followed by a rest period so that the bone marrow and other healthy tissues can recover. The approach was developed in 2000 from experiments in mice, and the term “metronomic” was coined at that time.[1]
Most metronomic regimens use older, inexpensive drugs taken by mouth, such as cyclophosphamide, methotrexate, capecitabine and vinorelbine.[1][2] Two examples from randomized trials show what the doses look like: cyclophosphamide 50 mg every day with methotrexate 2.5 mg twice a day on two days each week, for one year,[3] and capecitabine 650 mg per square meter of body surface twice a day without interruption for one year.[4]
Features and benefits of metronomic chemotherapy:
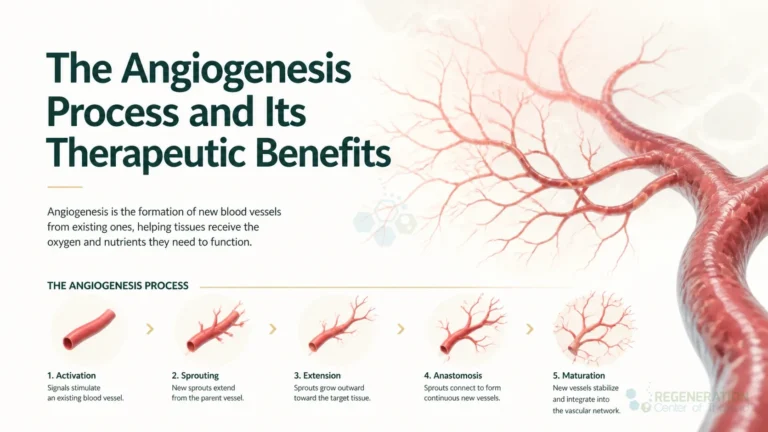
- Anti-angiogenic effect: Angiogenesis is the growth of new blood vessels from existing ones, which tumors need for oxygen and nutrients. In mice, frequent low doses of cyclophosphamide repeatedly killed the endothelial cells lining the tumor’s blood vessels, and this controlled tumors even when the cancer cells had been made resistant to the drug.[5] In mice carrying human neuroblastoma tumors, continuous low-dose vinblastine combined with an antibody against a receptor for the blood-vessel growth factor VEGF produced full and lasting regression of large tumors over more than six months of treatment, without obvious toxicity.[6]
- Immune effects: In people with advanced cancer, metronomic oral cyclophosphamide sharply reduced regulatory T cells, which damp down immune responses, and restored the activity of T cells and natural killer (NK) cells in blood samples.[7] This was a laboratory measurement in a small study, not a survival result.
- Direct effects on cancer cells: The drugs still act on the tumor cells themselves, alongside their effects on blood vessels, immune cells and the tumor’s surroundings.[1]
- Fewer severe side effects, though not none: Across 80 published studies, mostly in people with pretreated advanced breast and prostate cancer, severe (grade 3 or 4) side effects were uncommon, for example anemia in 7.8% and fatigue in 13.4%.[2] Side effects still occur, as the trials below show.
- Lower cost: Most of the drugs are generic and taken at home, which avoids infusions and hospital stays.[1] In a trial in India, an oral regimen of weekly methotrexate with daily celecoxib was compared with intravenous cisplatin for advanced head and neck cancer in a setting where the recommended newer drugs are often unaffordable.[8]
- Combinations: Metronomic schedules are studied alongside drugs that block blood-vessel growth, immunotherapy, targeted therapy, hormone therapy and radiotherapy.[1]
Metronomic therapy vs conventional chemotherapy
Conventional chemotherapy kills dividing cells, and the same drugs damage other fast-dividing cells in the body, in the bone marrow, hair follicles and lining of the gut, which is why rest periods are built in. Metronomic dosing shifts part of the effect from the cancer cells to the tumor’s blood vessels and immune environment.[1]
| Feature | Conventional (maximum tolerated dose) | Metronomic |
|---|---|---|
| Dose | Highest dose the patient can tolerate | Lowest dose with an anti-tumor effect |
| Schedule | Cycles with drug-free breaks for recovery | Continuous, often daily, without long breaks |
| Usual route | Often intravenous | Usually tablets taken at home |
| Main targets | Dividing cancer cells | Tumor blood vessels, immune cells and cancer cells |
| Typical use | Curative and palliative treatment of many cancers | Maintenance after standard treatment, palliative treatment and people unfit for intensive chemotherapy |
The comparison in the table follows a 2024 review.[1] Metronomic chemotherapy is not a replacement for standard treatment in general. In the positive trials below, it was given as maintenance after standard treatment, or as palliative treatment where the usual recommended drugs were not feasible.

What the Randomized Trials Show
A 2013 analysis of 80 metronomic studies found no completed phase III trial at that time, and could not identify which patients, doses or schedules respond best.[2] Phase III trials have since reported both positive and negative results. Published examples, largest first:
| Trial | Patients | Regimen | Result |
|---|---|---|---|
| IBCSG 22-00, early hormone receptor-negative breast cancer, after standard treatment | 1,081 | Low-dose cyclophosphamide and methotrexate for 1 year, or no maintenance | No significant improvement in disease-free survival after a median of 6.9 years[3] |
| CAIRO3, metastatic colorectal cancer, after initial chemotherapy | 558 | Maintenance capecitabine with bevacizumab, or observation | Time to second progression 11.7 vs 8.5 months; hand-foot reactions in 23%[9] |
| SYSUCC-001, early triple-negative breast cancer, after standard treatment | 434 analyzed | Low-dose capecitabine for 1 year, or observation | 5-year disease-free survival 82.8% vs 73.0%[4]; at 10 years, 78.1% vs 66.6%, with overall survival not significantly different (82.4% vs 73.7%)[10] |
| Recurrent or metastatic head and neck cancer, palliative treatment, India | 422 | Oral methotrexate and celecoxib, or intravenous cisplatin | Median overall survival 7.5 vs 6.1 months; severe side effects 19% vs 30%[8] |
| High-risk nasopharyngeal carcinoma, after chemoradiotherapy | 406 | Metronomic capecitabine for 1 year, or observation | 3-year failure-free survival 85.3% vs 75.7%; grade 3 side effects 17% vs 6%[11]; longer overall survival after a median of 71.3 months (hazard ratio 0.53)[12] |
| MECCA, hormone receptor-positive, HER2-negative metastatic breast cancer, first treatment for metastatic disease | 263 | Metronomic capecitabine plus an aromatase inhibitor, or the aromatase inhibitor alone | Median progression-free survival 20.9 vs 11.9 months; overall survival also longer (hazard ratio 0.58); grade 3 side effects in 15.1% with the combination[13] |
| Children with progressive solid tumors after at least two lines of chemotherapy | 108 | Four-drug oral metronomic regimen, or placebo | No improvement: 96.4% vs 100% had progressed by 6 months[14] |
For children and young adults with high-risk solid tumors outside the brain, a 2024 meta-analysis of three randomized trials with 775 participants found a survival hazard ratio of 0.75 in favor of metronomic chemotherapy, but the trials differed a great deal clinically and the authors advised caution.[15] In SYSUCC-001, hand-foot syndrome affected 45.2% of patients on capecitabine, 7.7% severely.[4]
Who Might Be Offered It
Metronomic chemotherapy has moved from a last option for heavily pretreated metastatic cancer to maintenance treatment after standard therapy for some high-risk cancers, on the strength of phase III trials.[1] Its low toxicity also makes it a possible option for older or frail patients and where cost limits access to other drugs.[1] No validated test yet predicts who will benefit, which makes patient selection difficult.[16]
Metronomic schedules still need the same monitoring as other chemotherapy, including blood counts and side effects, and the choice depends on the cancer type, its stage, earlier treatment and general health. That decision belongs with the treating oncologist. An overview of how cancer treatment is planned is on our oncology page.
Published Clinical Citations
[1] ^ Wu HL, Zhou HX, Chen LM, Wang SS. Metronomic chemotherapy in cancer treatment: new wine in an old bottle. Theranostics. 2024;14(9):3548-3564. https://doi.org/10.7150/thno.95619
[2] ^ Lien K, Georgsdottir S, Sivanathan L, Chan K, Emmenegger U. Low-dose metronomic chemotherapy: a systematic literature analysis. European Journal of Cancer. 2013;49(16):3387-3395. https://doi.org/10.1016/j.ejca.2013.06.038
[3] ^ Colleoni M, Gray KP, Gelber S, et al. Low-dose oral cyclophosphamide and methotrexate maintenance for hormone receptor-negative early breast cancer: International Breast Cancer Study Group Trial 22-00. Journal of Clinical Oncology. 2016;34(28):3400-3408. https://doi.org/10.1200/JCO.2015.65.6595
[4] ^ Wang X, Wang SS, Huang H, et al. Effect of capecitabine maintenance therapy using lower dosage and higher frequency vs observation on disease-free survival among patients with early-stage triple-negative breast cancer who had received standard treatment: the SYSUCC-001 randomized clinical trial. JAMA. 2021;325(1):50-58. https://doi.org/10.1001/jama.2020.23370
[5] ^ Browder T, Butterfield CE, Kräling BM, et al. Antiangiogenic scheduling of chemotherapy improves efficacy against experimental drug-resistant cancer. Cancer Research. 2000;60(7):1878-1886. https://pubmed.ncbi.nlm.nih.gov/10766175/
[6] ^ Klement G, Baruchel S, Rak J, et al. Continuous low-dose therapy with vinblastine and VEGF receptor-2 antibody induces sustained tumor regression without overt toxicity. Journal of Clinical Investigation. 2000;105(8):R15-R24. https://doi.org/10.1172/JCI8829
[7] ^ Ghiringhelli F, Menard C, Puig PE, et al. Metronomic cyclophosphamide regimen selectively depletes CD4+CD25+ regulatory T cells and restores T and NK effector functions in end stage cancer patients. Cancer Immunology, Immunotherapy. 2007;56(5):641-648. https://doi.org/10.1007/s00262-006-0225-8
[8] ^ Patil V, Noronha V, Dhumal SB, et al. Low-cost oral metronomic chemotherapy versus intravenous cisplatin in patients with recurrent, metastatic, inoperable head and neck carcinoma: an open-label, parallel-group, non-inferiority, randomised, phase 3 trial. The Lancet Global Health. 2020;8(9):e1213-e1222. https://doi.org/10.1016/S2214-109X(20)30275-8
[9] ^ Simkens LH, van Tinteren H, May A, et al. Maintenance treatment with capecitabine and bevacizumab in metastatic colorectal cancer (CAIRO3): a phase 3 randomised controlled trial of the Dutch Colorectal Cancer Group. The Lancet. 2015;385(9980):1843-1852. https://doi.org/10.1016/S0140-6736(14)62004-3
[10] ^ Yuan J, Bi XW, Hua X, et al. Metronomic capecitabine as extended adjuvant chemotherapy for early triple-negative breast cancer (SYSUCC-001): updated 10-year outcomes and post-hoc exploratory biomarker analysis from a randomised, phase 3 trial. The Lancet Oncology. 2025;26(12):1575-1583. https://doi.org/10.1016/S1470-2045(25)00545-5
[11] ^ Chen YP, Liu X, Zhou Q, et al. Metronomic capecitabine as adjuvant therapy in locoregionally advanced nasopharyngeal carcinoma: a multicentre, open-label, parallel-group, randomised, controlled, phase 3 trial. The Lancet. 2021;398(10297):303-313. https://doi.org/10.1016/S0140-6736(21)01123-5
[12] ^ Tao YL, Wu DH, Zhou Q, et al. Long-term outcomes of adjuvant metronomic capecitabine in locoregionally advanced nasopharyngeal carcinoma: a randomized, controlled, multicenter, phase 3 study. Nature Cancer. 2026;7(7):1149-1157. https://doi.org/10.1038/s43018-026-01193-4
[13] ^ Hong RX, Xu F, Xia W, et al. Metronomic capecitabine plus aromatase inhibitor as initial therapy in patients with hormone receptor-positive, human epidermal growth factor receptor 2-negative metastatic breast cancer: the phase III MECCA trial. Journal of Clinical Oncology. 2025;43(11):1314-1324. https://doi.org/10.1200/JCO.24.00938
[14] ^ Pramanik R, Agarwala S, Gupta YK, et al. Metronomic chemotherapy vs best supportive care in progressive pediatric solid malignant tumors: a randomized clinical trial. JAMA Oncology. 2017;3(9):1222-1227. https://doi.org/10.1001/jamaoncol.2017.0324
[15] ^ Peinemann F, Hoemberg M. Metronomic chemotherapy for paediatric extracranial solid tumours: a systematic review and meta-analysis of randomised clinical trials. BMJ Open. 2024;14(10):e084477. https://doi.org/10.1136/bmjopen-2024-084477
[16] ^ Wysocki PJ, Kwinta Ł, Wysocka E. Predictive biomarkers of metronomic chemotherapy response in solid tumors: chasing an elusive signal. Cancers. 2026;18(15):2488. https://doi.org/10.3390/cancers18152488